Ling Shu Nine Needling Methods: Navigating Nine-Pathology Depth Vectors, Contralateral Somatosensory Dynamics, and Precision Acupressure Protocols
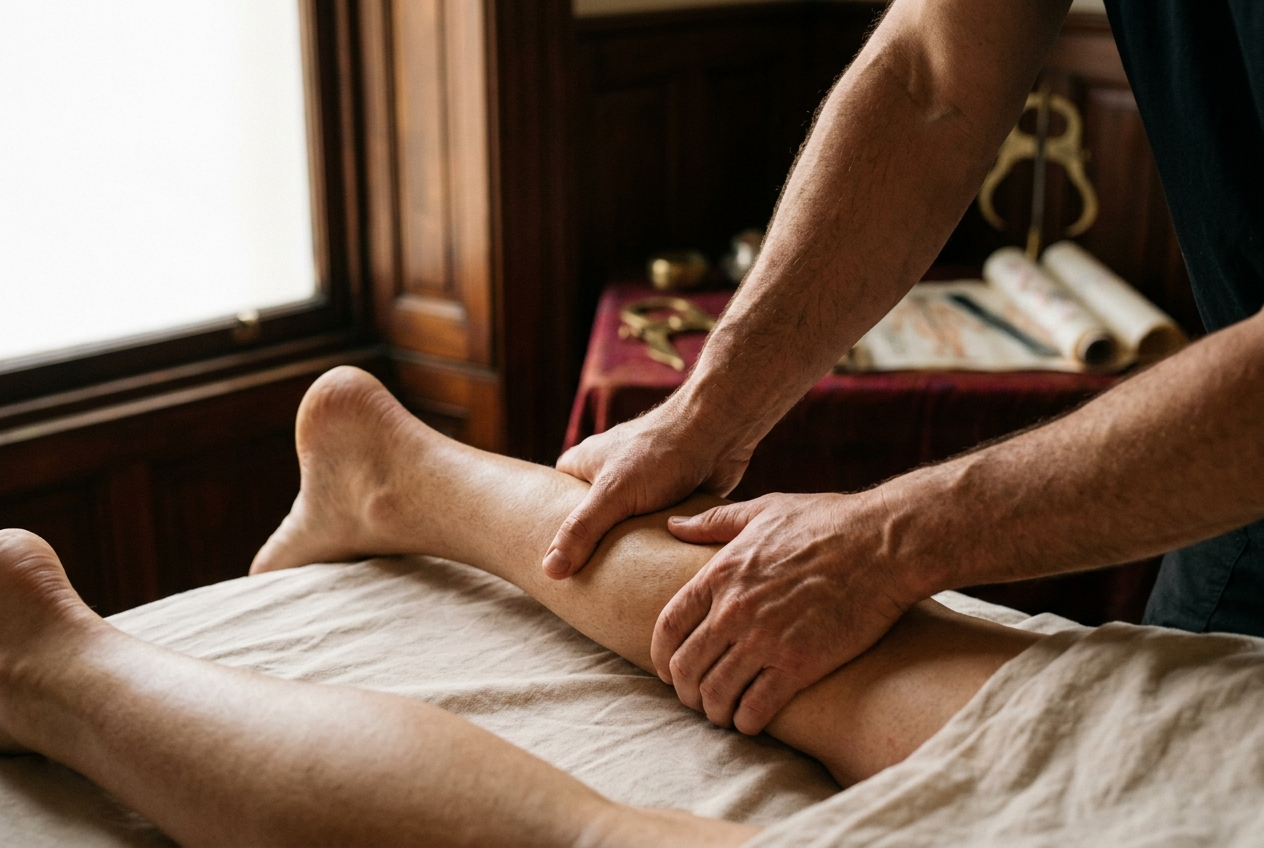
1. Opening — Somatosensory Mapping and the Lived Experience of Systemic Dysregulation
Every clinical presentation begins not as an abstract pathology, but as a tangible disruption in the patient's lived somatic experience. A desk worker presents with chronic cervicocranial tension, an intractable mid-thoracic dullness, and a persistent mid-afternoon digestive lethargy; a runner presents with lateral knee pain that defies local muscular treatment; an executive suffers from nocturnal hyperarousal, epigastric constriction, and cold extremities. Contemporary biomedical models frequently atomize these presentations into discrete, isolated diagnoses—tension headache, functional dyspepsia, iliotibial band friction syndrome, autonomic dysregulation.
Traditional Chinese Medicine (TCM), by contrast, conceptualizes these diverse dysfunctions as manifestations of depth-dependent morphological and bioenergetic imbalances along interconnected meridian trajectories.
The canonical foundation for understanding and resolving these multi-layered somatosensory patterns is codified in the Huangdi Neijing Ling Shu (The Yellow Emperor's Inner Classic: Spiritual Pivot), specifically in Chapter 7, entitled Guan Zhen (官针, "Official Needling"). Within this seminal discourse, classical physician-philosophers established the Nine Needling Methods (Jiu Ci / 九刺), an architectural taxonomy designed to treat the "Nine Pathological Variations" (Jiu Bian / 九变).
Rather than viewing the human soma as a homogenous mass, the Ling Shu presents the body as a stratified neurofascial and vascular continuum composed of distinct histological layers: 1. The epidermal and dermal envelope (Pi Mao / skin and hair), 2. The superficial and deep venous-microvascular networks (Luo Mai / collaterals), 3. The intermuscular fascial planes and muscular bellies (Fen Rou / divided flesh), 4. The tendinous and articular structures (Jin / sinews), and 5. The deep osseous and periosteal foundations (Gu / bone).
Contemporary neurobiology, mechanobiology, and fascia research—documented extensively in the biomedical literature on mechanotransduction in fascial acupuncture and connective tissue tensegrity—have validated this classical structural logic. Each of the Nine Needling Methods corresponds directly to a specific physical depth, a targeted sensory receptor population, and a distinct neural reflex arc.
By translating these nine classical invasive needling vectors into non-invasive, precision manual therapies (acupressure, ischemic compression, transverse fascial friction, cutaneous brushing, and contralateral tapping), clinicians and self-directed practitioners can engage these deep regulatory circuits with exceptional fidelity.
2. The Meridian Path — A Neurofascial Journey Through the Somatic Matrix
To understand how mechanical stimuli applied at the periphery can resolve internal organ dysfunction or chronic regional pain, one must trace the somatic highway of the meridians (Jing-Luo / 经络) not as esoteric lines drawn on parchment, but as continuous planes of connective tissue, neurovascular bundles, and dermatomal/myotomal maps.
Consider the Stomach Meridian of Foot-Yangming (Zu Yangming Wei Jing) and its anatomical counterpart, the Bladder Meridian of Foot-Taiyang (Zu Taiyang Pangguang Jing). The Yangming channel does not traverse arbitrary space; it follows the anterior functional movement chain.
The pathway initiates on the face just below the orbit, descends through the masseteric fascia, traverses down the sternocleidomastoid sheath into the supraclavicular fossa, plunges through the pectoralis major and the rectus abdominis sheath, navigates the deep interfascial septum between the rectus femoris and vastus lateralis, sweeps down the lateral border of the tibia (over the tibialis anterior muscle belly), and terminates at the lateral ungual angle of the second digit of the foot.
When a practitioner palpates this pathway, they are tracing an unbroken continuous myofascial track. Tension, fluid stasis, or neurogenic inflammation at the distal end of this pathway (such as the muscular junction of the anterior shin) creates retrograde mechanical pull along the entire fascial train, restricting the excursion of the thoracoabdominal diaphragm and altering visceral mechanoreceptor signaling.
Conversely, applying depth-calibrated mechanical pressure to designated nodal points (Acupoints / Xue Wei) along this pathway initiates piezoelectric potentials within the collagenous extracellular matrix, stimulates mechanosensitive ion channels (PIEZO1, PIEZO2, and TRPV channels), and triggers afferent somatic signaling that modulates dorsal horn gateway mechanisms in the spinal cord, as detailed by the World Health Organization Acupuncture Benchmarks.
3. The Nine Classical Needling Methods (Guan Zhen Jiu Ci): Exegesis, Neurobiology, and Acupressure Translation
Chapter 7 of the Ling Shu states:
“Nine are the methods of needling, each answering to one of the nine pathological variations: the first is Shu Needling; the second is Distant Needling; the third is Meridian Needling; the fourth is Collateral Needling; the fifth is Intermuscular Needling; the sixth is Great Draining Needling; the seventh is Hair Needling; the eighth is Contralateral Needling; the ninth is Heated Needling.” (《灵枢·官针》:凡刺有九,以应九变。一曰输刺,二曰远道刺,三曰经刺,四曰络刺,五曰分刺,六曰大泻刺,七曰毛刺,八曰巨刺,九曰焠刺。)
Below is the comprehensive analysis of each method, detailing its classical mandate, its cellular and neurophysiological substrate, and its exact translation into clinical acupressure.
3.1. Shu Needling (Shu Ci / 输刺) — The Deep Visceral-Somatic Conduit
Classical Exegesis & Pathological Indication
The Ling Shu defines Shu Ci:
“Shu Needling refers to puncturing the Shu points of the Five Zang organs and the deep somatic junctions to drain pathogenic heat and clear deep internal stagnation.”
Shu (输) carries the etymological meaning of "transporting" or "conveying." Classically, this method is deployed when visceral pathogenic heat, deep visceral distension, or deep chronic exhaustion resides within the Yin organ networks (Zang). It utilizes the Back-Shu points (Bei-Shu / 背输穴) along the medial branch of the Bladder channel, as well as the Five Transporting Shu points located distal to the elbows and knees.
Biomedical & Neurofascial Mechanisms
Anatomically, Back-Shu points lie directly over the dorsal rami of the thoracic and lumbar spinal nerves, adjacent to the sympathetic paravertebral chain. When mechanical force penetrates through the trapezius, rhomboids, and erector spinae muscle layers, it stimulates group III (A-delta) and group IV (C) afferent fibers embedded within the deep thoracolumbar fascia.
These signals enter the spinal dorsal horn at the exact metamere (neurological segment) corresponding to the sympathetic innervation of the target internal organ (e.g., T5 for Heart, T9 for Liver, T12 for Spleen/Stomach).
This induces a somatovisceral reflex, dampening sympathetic hypertonicity, reducing visceral vasospasm, and normalizing splanchnic perfusion, as corroborated by research in neurobiological mechanisms of acupuncture.
Precision Acupressure Translation
- Manual Vector: Perpendicular, sustained, deep static compression (An Fa / 按法 combined with Chen Fa / 沉法).
- Target Loci: BL13 (Feishu), BL18 (Ganshu), BL20 (Pishu), BL23 (Shenshu).
- Execution Protocol: The clinician uses the reinforced thumb tip or the olecranon process (elbow apex) angled at exactly 90 degrees to the paraspinal lamina groove. Pressure is applied gradually over 10 seconds until reaching the dense, resilient deep paraspinal fascial bed.
- Dosage & Sensation: Maintain sustained ischemic pressure for 90 to 180 seconds while the patient performs slow, diaphragmatic exhalations. The sensation must be a profound, dull, radiating ache (De Qi) that wraps laterally around the rib cage or penetrates anteriorly into the visceral cavity, completely devoid of sharp, superficial pain.
3.2. Distant Needling (Yuan Dao Ci / 远道刺) — Axial-Appendicular Distal Signaling
Classical Exegesis & Pathological Indication
The Ling Shu dictates:
“Distant Needling refers to puncturing points on the lower extremities to treat disorders residing in the upper trunk, head, face, and internal organs.”
This fundamental principle reflects the profound bidirectional somatotopic organization of the meridian system: pathologies of the zenith (the head, sensory orifices, chest) are regulated by manipulating the nadir (the strong motor points and dense sensory fields of the feet and lower legs).
Biomedical & Neurofascial Mechanisms
The neurobiological rationale for Yuan Dao Ci centers on Diffuse Noxious Inhibitory Controls (DNIC) and the recruitment of long ascending sensory pathways (the spinothalamic and spinoreticular tracts). Distal extremity loci possess extraordinarily high receptive field densities and a high concentration of encapsulated mechanoreceptors and nerve trunks (e.g., the common fibular, tibial, and deep peroneal nerves).
Afferent volleys generated at the anterior compartment of the lower leg (e.g., ST36) travel rostrally through the spinal cord to the periaqueductal gray (PAG) and the rostral ventromedial medulla (RVM) in the brainstem. This triggers descending serotonergic and noradrenergic pain-modulating pathways, which broadly suppress nociceptive gate transmission across cervical and cranial dermatomes while simultaneously dampening hyperactive central autonomic drive.
Precision Acupressure Translation
- Manual Vector: Distal-to-proximal angled compression with rhythmic micro-rotation.
- Target Loci: ST36 (Zusanli), SP6 (Sanyinjiao), LV3 (Taichong), KD1 (Yongquan).
- Execution Protocol: Position the thumb or a polished rounded wooden acupressure tool against the distal border of the point. Apply continuous, heavy compression while angling the force vector 15 degrees proximally (toward the trunk). Maintain for 2 minutes per limb.
- Dosage & Sensation: Strong, heavy distension that propagates proximally along the anterior tibial crest or up the medial aspect of the thigh toward the lower abdomen.
3.3. Meridian Needling (Jing Ci / 经刺) — The Longitudinal Tract Method
Classical Exegesis & Pathological Indication
The Ling Shu notes:
“Meridian Needling refers to puncturing the principal channel vessels directly where palpable indurations, nodulations, or stagnations reside along the meridian pathway.”
Unlike distal or visceral approaches, Jing Ci directly addresses the structural, palpable pathology along the primary meridian channel (Jing Mai). It is indicated for channel-specific blockages, tracking pain, numbness, and fascial densifications that follow the precise trajectory of a single meridian.
Biomedical & Neurofascial Mechanisms
Jing Ci operates at the level of the epimysial and perimysial fascial sheaths that envelop functional muscle groups. Research in fascial physiology indicates that chronic mechanical overuse or localized ischemia causes cross-linking of collagen fibrils and densification of hyaluronan within the deep fascia. This structural stiffening impairs fascial gliding and irritates nociceptive free nerve endings.
Applying targeted force along these longitudinal pathways generates shear strain between connective tissue layers, initiating a piezoelectric "sol-to-gel" transformation in the ground substance, restoring inter-fascial mobility, and accelerating the clearance of localized pro-inflammatory neuropeptides (substance P and calcitonin gene-related peptide / CGRP).
Precision Acupressure Translation
- Manual Vector: Longitudinal deep myofascial stripping and transverse cross-fiber mobilization (Rou Fa / 揉法 combined with Tui Fa / 推法).
- Target Loci: Palpable bands along the Gallbladder channel (e.g., GB31 to GB34 on the lateral thigh) or the Large Intestine channel (e.g., LI10 to LI11 on the extensor forearm).
- Execution Protocol: Lubricate the skin with a minimal amount of botanical oil. Place the reinforced thumb pad or distal hypothenar eminence directly into the interfascial groove of the channel. Apply sustained, deep pressure and slowly glide along the channel tract over 6 to 10 inches, moving at a speed of approximately 1 inch per second. Repeat 10 to 15 times per tract.
- Dosage & Sensation: A "good hurt" characterized by intense local warmth and the palpable release of taut bands or "grittiness" within the deep fascial tissue.
3.4. Collateral Needling (Luo Ci / 络刺) — Microvascular Decompression
Classical Exegesis & Pathological Indication
The Ling Shu establishes:
“Collateral Needling refers to puncturing the superficial small collaterals to discharge stagnant, darkened blood and expel pathogenic heat and stasis.”
Luo Ci targets the collateral network (Luo Mai), specifically visible, engorged, purple or crimson micro-venules. It is the classical method of micro-bloodletting, deployed to treat severe local blood stasis (Xue Yu), acute febrile conditions, acute severe swelling, or deep mental agitation arising from collateral obstruction.
Biomedical & Neurofascial Mechanisms
The microvascular bed targeted by Luo Ci comprises post-capillary venules and subpapillary venous plexuses where blood flow has become sluggish, leading to local hypoxia, hypercapnia, and acidosis.
In classical therapy, microscopic puncturing releases this high-pressure microvascular pool. In non-invasive manual medicine, the same microcirculatory reset is achieved via centripetal compressive flushing and microvascular shear stress.
This mechanical stimulus stretches the vascular endothelium, upregulating endothelial nitric oxide synthase (eNOS), inducing robust local vasodilation, flushing out acidic inflammatory exudates, and promoting immediate tissue re-oxygenation.
Precision Acupressure Translation
- Manual Vector: Rhythmic, high-velocity centripetal pumping and localized micro-compression (Ji Fa / 挤法 and Tui Fa / 推法).
- Target Loci: Spider-vein clusters at the popliteal fossa (BL40 / Weizhong), the thenar eminence (LU10 / Yuji), or the apex of the ear.
- Execution Protocol: Identify the area of microvascular congestion. Using the broad surface of the thumb, apply firm, rhythmic strokes directed strictly toward the heart (centripetal direction) at a cadence of 2 strokes per second for 60 seconds. Follow immediately with sustained static compression on the primary supplying node for 30 seconds.
- Dosage & Sensation: Moderate, rhythmic pressure that causes immediate visible blanching of the tissue followed by a rapid, warm, hyperemic reactive flush upon release.
3.5. Intermuscular Needling (Fen Ci / 分刺) — Myofascial Septum and Trigger Point Release
Classical Exegesis & Pathological Indication
The Ling Shu dictates:
“Intermuscular Needling refers to inserting the needle into the spaces between muscular boundaries and fleshy clefts to treat muscular Bi syndrome, pain, and spasms.”
Fen (分) translates to "dividing" or "cleaving." This method specifically targets the distinct boundaries between individual muscle bellies (Fen Rou / 分肉) and the deep myofascial trigger points (MTrPs) embedded within contracted muscle fibers. It is indicated for structural muscular cramping, focal myofascial pain syndromes, and movement limitations caused by myofascial adhesions.
Biomedical & Neurofascial Mechanisms
Intermuscular clefts are the primary anatomical corridors through which major neurovascular bundles traverse. Pathologically, sustained muscle contraction causes localized energy crises, excessive acetylcholine release at the motor endplate, and continuous sarcomere shortening—the hallmark of a Myofascial Trigger Point.
Inserting a mechanical vector directly into these intermuscular clefts physically separates adhered fascial investing layers, breaks the abnormal actin-myosin contracture cycle, normalizes intracellular calcium concentrations, and eliminates abnormal motor endplate noise.
Precision Acupressure Translation
- Manual Vector: Pincer palpation and deep perpendicular ischemic compression (Na Fa / 拿法 and Zhua Fa / 抓法).
- Target Loci: Intermuscular groove between the extensor carpi radialis and extensor digitorum communis (LI10 / Shousanli), or the cleft between the gastrocnemius heads (BL57 / Chengshan).
- Execution Protocol: Grasp the targeted muscle belly using the thumb and opposing index/middle fingers. Isolate the exact indurated, hyperirritable taut band within the cleft. Compress the band firmly until tissue resistance is encountered. Hold without movement for 60 to 90 seconds until a distinct softening or "melting" sensation is perceived beneath the fingers.
- Dosage & Sensation: Intense, localized dull ache accompanied by a brief local twitch response (fasciculation), followed by immediate muscular relaxation and restored joint range of motion.
3.6. Great Draining Needling (Da Xie Ci / 大泻刺) — Evacuative Tension Decompression
Classical Exegesis & Pathological Indication
The Ling Shu states:
“Great Draining Needling refers to using the broad lancet needle (Pizhen / 铍针) to evacuate purulent matter, drain massive fluid accumulations, and relieve severe focal swelling.”
Historically, this was the ancient surgical method for draining abscesses, large hematomas, and severe peripheral edema. In modern, non-invasive applications, Da Xie Ci represents the rapid evacuation of acute inflammatory fluid stasis, high-pressure compartmental tension, and severe lymphatic congestion.
Biomedical & Neurofascial Mechanisms
Interstitial edema elevates hydrostatic tissue pressure, compressing micro-lymphatics and local capillaries. This traps cellular debris, lactic acid, and inflammatory cytokines (TNF-alpha, IL-6), creating a vicious cycle of persistent pain and tissue induration.
By applying broad-surface, graduated hydrostatic compression along anatomical lymphatic channels, the practitioner mechanically forces fluid into the initial lymphatics, opens anchoring filaments, accelerates lymphatic return, and immediately reduces tissue turgor.
Precision Acupressure Translation
- Manual Vector: Broad-contact, slow, rhythmic retrograde effleurage and graduated broad-palm decompression (Mo Fa / 摩法 and Tui Fa / 推法).
- Target Loci: Swollen periarticular zones, such as the peri-malleolar region (around KD3/BL60) or the supraclavicular and axillary lymphatic drainage basins.
- Execution Protocol: Elevate the affected limb slightly. Using the broad palms of both hands, encircle the swollen compartment. Apply a gentle, rhythmic, wave-like compression directed toward the proximal lymph nodes (e.g., from the ankle toward the popliteal fossa, or from the wrist toward the axilla). Maintain a slow frequency of 1 stroke every 3 to 4 seconds for 3 to 5 minutes.
- Dosage & Sensation: Gentle to moderate pressure (never painful), producing a sensation of lightness, reduced tightness, and immediate subjective decompression.
3.7. Hair Needling (Mao Ci / 毛刺) — Superficial Somatosensory Neuromodulation
Classical Exegesis & Pathological Indication
The Ling Shu states:
“Hair Needling refers to shallow, multi-point tapping over the very superficial layers of the skin, where the body hair resides, to treat superficial numbness, paresthesia, and cutaneous disharmonies.”
Mao Ci operates strictly at the outermost boundary of the organism—the epidermis and the papillary dermis. It treats superficial sensory deficits, hyperesthesia, localized itch, and early-stage exogenous pathogenic invasions lingering at the defensive exterior (Wei Qi / 卫气 level).
Biomedical & Neurofascial Mechanisms
The epidermis and papillary dermis are densely populated with low-threshold, rapidly adapting A-beta (Aβ) mechanoreceptors (Meissner corpuscles, Merkel discs) and non-peptidergic C-tactile (CT) afferents.
Stimulating these superficial receptors generates a high-frequency afferent barrage that excites inhibitory enkephalinergic interneurons in the substantia gelatinosa (Lamina II of the spinal dorsal horn).
This closes the pain gate (Melzack & Wall's Gate Control Theory), presynaptically inhibiting ascending transmission from small unmyelinated nociceptive A-delta and C fibers while activating central oxytocinergic and parasympathetic pathways via C-tactile signaling.
Precision Acupressure Translation
- Manual Vector: High-speed, feather-light cutaneous brushing and rapid superficial tapotement (Sao Fa / 扫法 and Kou Fa / 叩法).
- Target Loci: Cutaneous dermatomes overlying the upper back (BL12 / Fengmen region), the forehead and glabella (GV24 / Yintang), or areas of superficial neural hypersensitivity.
- Execution Protocol: Using the soft fingertips or a stiff natural bristle brush, stroke the surface of the skin with minimal downward pressure—just enough to deflect the fine vellus hairs without depressing the subcutaneous tissue. Move rapidly in cross-hatching or circular patterns at a rate of 3 to 5 strokes per second for 60 to 90 seconds.
- Dosage & Sensation: A light, tingling, pleasurable somatosensory wave; immediate alleviation of local cutaneous burning, itching, or hyperalgesia.
3.8. Contralateral Needling (Ju Ci / 巨刺) — Trans-Hemispheric & Commissural Neuromodulation
Classical Exegesis & Pathological Indication
The Ling Shu dictates:
“Contralateral Needling refers to puncturing points on the left side of the body when the pathology is on the right side, and puncturing points on the right side when the pathology is on the left.”
Ju Ci is the classical doctrine of contralateral cross-treatment. It is strictly indicated for unilateral conditions: acute hemilateral musculoskeletal trauma, unilateral stroke rehabilitation, severe unilateral migraine, and localized limb pain where the affected side is too inflamed, traumatized, or hypersensitive to tolerate direct touch.
Biomedical & Neurofascial Mechanisms
The neurological substrate of Ju Ci involves commissural interneurons in the spinal cord and interhemispheric cortical communication via the corpus callosum. Sensory inputs entering the dorsal horn on one side of the body project via commissural interneurons across the anterior white commissure to modulate motor and sensory neuronal pools on the contralateral side, as detailed in studies on spinal cord cross-reflex pathways.
Furthermore, functional MRI studies demonstrate that strong somatosensory stimulation of an unaffected limb alters the receptive field topology of the primary somatosensory cortex (S1) and primary motor cortex (M1) of the opposite hemisphere, breaking central unilateral pain loops without risking local tissue irritation at the injured site.
Precision Acupressure Translation
- Manual Vector: Contralateral mirror-point ischemic compression combined with synchronized active movement of the injured side (Dong Qi / 动气法).
- Target Loci: Contralateral homologous anatomical points (e.g., right LI4 for left facial/dental pain; right LV3 for acute left hypochondriac spasm; right GB34 for left shoulder impingement).
- Execution Protocol: Identify the precise tender focus on the pathological side (e.g., severe acute left lateral epicondylitis at LI11). Locate the identical anatomical point on the completely pain-free right limb. Apply strong, steady ischemic compression to the healthy right point. While maintaining this compression, instruct the patient to slowly and actively mobilize the affected left limb through its pain-free range of motion for 90 seconds.
- Dosage & Sensation: Intense, sharp-dull sensation on the healthy limb; simultaneous rapid reduction in pain and expansion of motion on the injured side.
3.9. Heated Needling (Cui Ci / 焠刺) — Thermal Mechanotransduction & Rheological Remodeling
Classical Exegesis & Pathological Indication
The Ling Shu states:
“Heated Needling refers to heating the needle red-hot in a flame and rapidly inserting it to treat cold-induced Bi syndrome, deep tendinous contractures, bone spurs, and chronic intractable joint stagnation.”
Cui Ci (also known as Huo Zhen / 火针 or Fire Needling) is the classical application of targeted, high-intensity thermal energy into dense connective tissues. It is indicated for cold-damp obstruction (Han Shi Bi), chronic calcific tendinopathies, thickened joint capsules, and recalcitrant, deep-seated myofascial pain that worsens with cold and dampness.
Biomedical & Neurofascial Mechanisms
Dense fibrous connective tissues (tendons, ligaments, periosteal entheses) possess low vascularity and high concentrations of dense type-I collagen. Pathologically, chronic cold and microtrauma cause the collagenous matrix to become stiff and poorly hydrated.
Thermal stimulation triggers TRPV1 (transient receptor potential vanilloid 1) ion channels on sensory nerve endings, inducing a localized neurogenic inflammatory response that floods the avascular tendon with substance P and CGRP, stimulating neo-angiogenesis and fibroblast proliferation.
Simultaneously, heat alters the thixotropic state of the ground substance, liquefying stiffened proteoglycan matrices and restoring viscoelastic compliance to the tendon.
Precision Acupressure Translation
- Manual Vector: High-friction thermal acupressure (Cai Fa / 擦法) or localized heated compressive application using pre-heated smooth basalt tools or thermal moxa-analog manual pressure.
- Target Loci: Dense tendinous insertions, such as the Achilles tendon insertion (KD3/BL60 junction), the patellar ligament (ST35 / Dubi), or the supraspinatus tendon insertion (LI15 / Jianyu).
- Execution Protocol: Warm a smooth, rounded basalt acupressure stone in hot water (42°C–45°C / 108°F–113°F). Place the heated apex directly over the targeted tendinous enthesis. Apply deep, static compression combined with rapid, localized circular friction (2 to 3 revolutions per second) for 2 to 3 minutes until intense, deep thermal penetration is felt deep within the joint capsule.
- Dosage & Sensation: A profound, spreading, comfortable heat that penetrates through the tendon to the bone; immediate relief of stiffness and aching upon joint mobilization.
4. Mastering the Five Core Acupoints: Anatomical Palpation, De Qi Signatures, and Precision Vectors
To execute these clinical translations, the practitioner must possess unshakeable precision in locating and engaging the body's primary regulatory nodes. The five points below represent quintessential clinical anchors capable of receiving the Nine Needling vectors.
4.1. ST36 (Zusanli / 足三里) — "Leg Three Miles"
- Palpatory Location: Locate the lower border of the kneecap (patella). Move four finger-widths directly down the front of the shinbone. Slide your finger one finger-width toward the outside of the leg into the fleshy, muscular groove of the tibialis anterior.
- The Tactile De Qi Sensation: When the point is engaged at the correct intermuscular depth (Fen Ci / Yuan Dao Ci), the patient will experience a profound, heavy, dull ache that propagates down the shin to the dorsum of the foot, often accompanied by an audible gurgling in the abdomen (borborygmus).
- Manual Vector & Duration: Apply firm, perpendicular, distal-to-proximal angled pressure using the reinforced thumb. Maintain for 2 to 3 minutes per side.
- Clinical Scope: Epigastric distension, postprandial fatigue, general lethargy, systemic immune enhancement, lower-limb weakness.
4.2. LV3 (Taichong / 太冲) — "Great Surge"
- Palpatory Location: Place your finger in the webbing between your big toe and second toe. Slide your finger upward along the top of the foot toward the ankle for approximately two finger-widths until your finger drops into a distinct, sensitive, V-shaped hollow just before the two metatarsal bones join.
- The Tactile De Qi Sensation: Highly sensitive and reactive. A distinct, spreading, slightly sharp ache that quickly transforms into a soothing, heavy warmth radiating across the sole of the foot.
- Manual Vector & Duration: Perpendicular, deep static compression with gentle circular micro-rotation (Shu Ci / Ju Ci). Hold for 90 to 120 seconds.
- Clinical Scope: Acute stress hyperarousal, temporal headaches, irritability, visual fatigue, menstrual cramping, muscular spasms.
4.3. LI4 (Hegu / 合谷) — "Joining Valleys"
- Palpatory Location: Bring the thumb and index finger together; a prominent fleshy mound will form on the back of the hand. Place your opposite thumb at the peak of this mound. Now relax the hand, and angle your thumb inward toward the bone of the second finger (second metacarpal), pressing directly against the radial osseous border.
- The Tactile De Qi Sensation: A powerful, deep, heavy distension that "grasps" the thumb, often sending a warm, radiating sensation up the forearm toward the elbow or up into the jaw.
- Manual Vector & Duration: Angled compression directed firmly toward the bone (Jing Ci / Ju Ci). Hold with sustained, pulsating pressure (5 seconds on, 2 seconds off) for 2 minutes.
- Clinical Scope: Frontal headaches, dental/jaw tension, sinus congestion, acute upper-body musculoskeletal pain, emotional stagnation.
4.4. SP6 (Sanyinjiao / 三阴交) — "Three Yin Intersection"
- Palpatory Location: Locate the highest point of your inner ankle bone (medial malleolus). Lay four fingers horizontally across the inner lower leg, starting from the ankle bone. Directly above the top finger, in the deep groove just behind the rear border of the shinbone (tibia), lies SP6.
- The Tactile De Qi Sensation: A rich, tender, radiating ache that ascends along the inner border of the calf and thigh into the lower abdomen.
- Manual Vector & Duration: Deep, sustained static compression angled slightly forward under the posterior edge of the tibia (Shu Ci / Yuan Dao Ci). Maintain for 2 minutes.
- Clinical Scope: Pelvic floor dysregulation, dysmenorrhea, insomnia, lower abdominal bloating, fluid retention, anxiety.
4.5. PC6 (Neiguan / 内关) — "Inner Gate"
- Palpatory Location: Turn your palm upward. Locate the main crease of the wrist. Lay three fingers across the inside of the forearm, starting from the wrist crease. At the level of the third finger, in the exact center of the arm between the two prominent, rope-like tendons (flexor carpi radialis and palmaris longus), lies PC6.
- The Tactile De Qi Sensation: A subtle, electric-like or spreading warm sensation that radiates up through the chest or down into the palm of the hand.
- Manual Vector & Duration: Perpendicular, deep pincer compression using the thumb on PC6 and the index finger on the dorsal forearm opposite (Mao Ci / Shu Ci). Maintain for 90 seconds while practicing slow, deep respiration.
- Clinical Scope: Nausea, motion sickness, cardiac palpitations, chest tightness, acute emotional panic, diaphragmatic constriction.
5. Translational Clinical Protocols: Step-by-Step Scenario Applications
Below are three didactic, ready-to-execute clinical protocols translating the Ling Shu Nine Needling Methods into non-invasive, multi-nodal acupressure sequences for common contemporary pathologies.
Protocol 1: Acute Cervicobrachial Desk Strain and Trapezius Spasm
Target Presentation: Unilateral upper trapezius spasm, levator scapulae contracture, and occipital headache following prolonged computer posture.
- Step 1 — Contralateral Neuromodulation (Ju Ci): - If the left shoulder is locked in spasm, do not touch the left shoulder first. - Locate LI4 on the right hand (the healthy, opposite limb). - Apply heavy, sustained ischemic compression to right LI4 (Newtonian force: 25–35 N). - While maintaining this intense pressure, instruct the patient to slowly turn their head to the left, tilting the ear toward the left shoulder. Continue this combined mobilization for 90 seconds. - Result: Spinal commissural reflex arcs immediately suppress the protective hyper-reflexic spasm in the left cervical musculature.
- Step 2 — Intermuscular Fascial Release (Fen Ci): - Move to the affected left side. Locate GB20 (Fengchi) in the suboccipital depression between the trapezius and sternocleidomastoid attachments. - Apply deep, upward-and-inward pincer compression directly into the intermuscular cleft. - Hold static pressure for 90 seconds until the suboccipital band softens.
- Step 3 — Superficial Cutaneous Gate Sweep (Mao Ci): - Using the fingertips of both hands, perform high-speed, light cutaneous brushing from the base of the skull down over the top of the shoulder to the acromion process. - Execute at a rate of 4 strokes per second for 60 seconds. - Result: A-beta mechanoreceptor excitation abolishes residual burning sensation and restores full cervical rotation.
Protocol 2: Postprandial Gastric Stagnation & Functional Dyspepsia
Target Presentation: Severe epigastric fullness, abdominal bloating, slow digestion, and mental fog following a heavy or irregular meal.
- Step 1 — Distal Gastric Motility Activation (Yuan Dao Ci): - Have the patient seated comfortably with knees bent at 90 degrees. - Locate ST36 (Zusanli) bilaterally on the anterior shins. - Position both thumbs over the points, angling the force vector 15 degrees upward toward the knee. - Apply firm, rhythmic, sustained compression for 120 seconds per side. - Result: Recruits vagal efferent pathways via the brainstem, stimulating gastric peristalsis and acid-base balancing.
- Step 2 — Splanchnic Somatovisceral Modulation (Shu Ci): - Move to SP6 (Sanyinjiao) on the medial lower legs. - Apply deep, steady compression into the retro-tibial fascial groove for 90 seconds. - Coordinate with deep abdominal inhalation (expand belly) and complete exhalation.
- Step 3 — Periumbilical Microvascular Pumping (Luo Ci): - Place the warm heel of the hand directly over the epigastrium (CV12 / Zhongwan) and perform a wide, clockwise circular pumping motion around the umbilicus. - Apply moderate downward pressure on the descent (right abdomen) and light pressure on the ascent (left abdomen) for 2 minutes. - Result: Mechanical clearance of localized portal-splenic microvascular congestion and immediate relief of epigastric pressure.
Protocol 3: Sympathetic Hyperarousal, Anxiety & Nocturnal Insomnia
Target Presentation: Racing thoughts, chest tightness, resting tachycardia, inability to enter deep slow-wave sleep.
- Step 1 — C-Tactile Neuromodulation (Mao Ci): - The patient lies supine in a darkened, quiet environment. - Position the index or middle fingertip lightly at Yintang (Hall of Impression / Glabella). - Perform feather-light, slow downward strokes (3 cm/sec) from the mid-forehead down to the bridge of the nose for 90 seconds. - Result: Activates low-threshold unmyelinated C-tactile fibers, driving immediate parasympathetic vagal dominance and dampening the hyperactive amygdala.
- Step 2 — Pericardial Calming Compression (Shu Ci): - Locate PC6 (Neiguan) on both forearms. - Apply gentle, steady, deep compression into the intertendinous space for 90 seconds per arm. - Instruct the patient to inhale through the nose for 4 seconds, hold for 4 seconds, and exhale smoothly through the mouth for 7 seconds. - Result: Downregulates cardiac sympathetic outflow, stabilizing heart rate variability (HRV).
- Step 3 — Grounding Distal Somatosensory Reset (Ju Ci / Yuan Dao Ci): - Transition to LV3 (Taichong) on both feet. - Apply heavy, downward, grounding compression into the metatarsal V-groove for 120 seconds. - Result: Re-establishes peripheral somatosensory grounding, draws hyperactive blood flow away from the cerebral cortex, and promotes rapid sleep onset.
6. Comprehensive Comparative Diagnostic & Treatment Matrix
The following matrix serves as an exhaustive pedagogical synthesis of the Nine Needling Methods, providing a definitive roadmap from classical pathology to modern neurobiology and non-invasive acupressure execution.
7. Clinical Safety, Contraindications, Pressure Dosages, and Red Flags
The clinical mastery of depth-stratified somatosensory stimulation requires not only an understanding of technique, but an uncompromising commitment to physiological safety and diagnostic discrimination.
7.1. Pressure Dosage & Tactile Boundaries
- Superficial Cutaneous (Mao Ci): Apply between 0.5 to 2 Newtons of force. The skin should not blanch significantly; the mechanical vector should merely deflect epidermal hair follicles and stimulate low-threshold Aβ and C-tactile mechanoreceptors.
- Intermuscular / Myofascial (Fen Ci, Jing Ci): Apply between 15 to 30 Newtons of force. The tissue will blanch, and the clinician will feel the resistance of the deep fascia. The sensation should be a strong, tolerable, non-sharp ache (De Qi).
- Deep Somatovisceral / Periosteal (Shu Ci, Yuan Dao Ci): Apply between 30 to 45 Newtons of force. Pressure must be introduced slowly (over 10–15 seconds) to allow the visceral protective reflexes to relax rather than guard. Never exceed the threshold where the patient involuntarily winces, holds their breath, or exhibits muscular guarding.
7.2. Strict Contraindications & Special Populations
- Obstetric Precautions: - Strict absolute contraindication against heavy, downward, or dispersing acupressure on LI4 (Hegu), SP6 (Sanyinjiao), BL60 (Kunlun), GB21 (Jianjing), and the sacral foramen points (BL31–BL34 / Baliao) during pregnancy. - These points strongly stimulate uterine contractility via sacral parasympathetic and pelvic splanchnic pathways and can induce premature labor.
- Vascular Vulnerabilities: - Never apply deep compression (Shu Ci, Fen Ci) or vigorous friction over areas of suspected Deep Vein Thrombosis (DVT), severe varicose veins, phlebitis, or advanced peripheral vascular disease. - Avoid direct, heavy pressure over the carotid sinus (anterior neck) or major arterial bifurcations.
- Dermatological & Structural Compromise: - Avoid open wounds, unhealed surgical incisions, acute skin infections (cellulitis, erysipelas), localized burns, or un-stabilized bone fractures.
7.3. Clinical Red Flags Demanding Immediate Medical Referral
Self-administered or manual acupressure must never delay life-saving emergency medical or surgical intervention. Refer immediately to an emergency physician if any of the following are present: - Cardiovascular Red Flags: Crushing retrosternal chest pain radiating to the jaw, neck, or left arm; sudden severe shortness of breath; unexplained diaphoresis (cold sweats). - Neurological Red Flags: Sudden severe "thunderclap" headache; unilateral facial droop, arm weakness, or speech slurring (signs of acute ischemic or hemorrhagic stroke); sudden loss of vision. - Abdominal/Surgical Red Flags: Acute, rigid, board-like abdomen with severe rebound tenderness (peritoneal sign / visceral perforation); pulsatile abdominal mass; high fever accompanied by severe right lower quadrant pain (appendicitis).
8. Today's Takeaway: The Two-Minute Desk Reset
For the reader seeking immediate, tangible engagement with this classical system before closing this monograph, execute this rapid somatic recalibration:
By systematically uniting the classical anatomical wisdom of the Ling Shu with contemporary neurophysiology, clinicians and discerning practitioners transcend superficial symptom management—accessing the deep, elegant architecture of the human nervous system through the timeless science of somatic touch.
Authoritative Biomedical References & Further Reading
- World Health Organization: Benchmarks for the Practice of Acupuncture — Definitive global standards on point safety, anatomical depth, and clinical indications.
- National Center for Biotechnology Information (NCBI PubMed): Neurobiological Mechanisms of Acupuncture — Peer-reviewed investigation into central nervous system modulation, spinal reflex arcs, and somatosensory signaling.
- PMC: Mechanotransduction in Fascial Acupuncture — Detailed research on connective tissue deformation, fibroblast remodeling, and interstitial piezoelectricity.
- ScienceDirect: Connective Tissue and Fascial Tensegrity — Biomechanical review of myofascial continuities and shear-plane mechanics in manual therapies.
- NCBI PubMed: Cross-Spinal Reflex Circuits and Contralateral Neuromodulation — Experimental evidence for commissural interneuron activation underlying contralateral therapeutic modalities.
- Wikipedia: Traditional Chinese Medicine & Meridian Theory — Comprehensive historical and conceptual overview of the canonical classics and channel systems.