Nian Zhuan Fa: Navigating Twirling-Rotating Torque Dynamics, Fascial Shearing Mechanotransduction, and Precision Acupressure Protocols
If you have spent your afternoon staring into the phosphor glow of a monitor, you are likely intimately familiar with a specific somatic pattern: a dull, vise-like tightening at the base of the skull, a clenched jaw, a knot of digestive stagnation beneath the diaphragm, and a shallow, restless breathing pattern. We routinely dismiss these discomforts as the unavoidable tax of modern cognitive labor. Yet within the diagnostic taxonomy of Traditional Chinese Medicine (TCM), these disparate symptoms map precisely to neurovascular and fascial constrictions along the primary channel pathways—most notably the Stomach (Yangming), Large Intestine, Liver (Jueyin), and Pericardium networks.
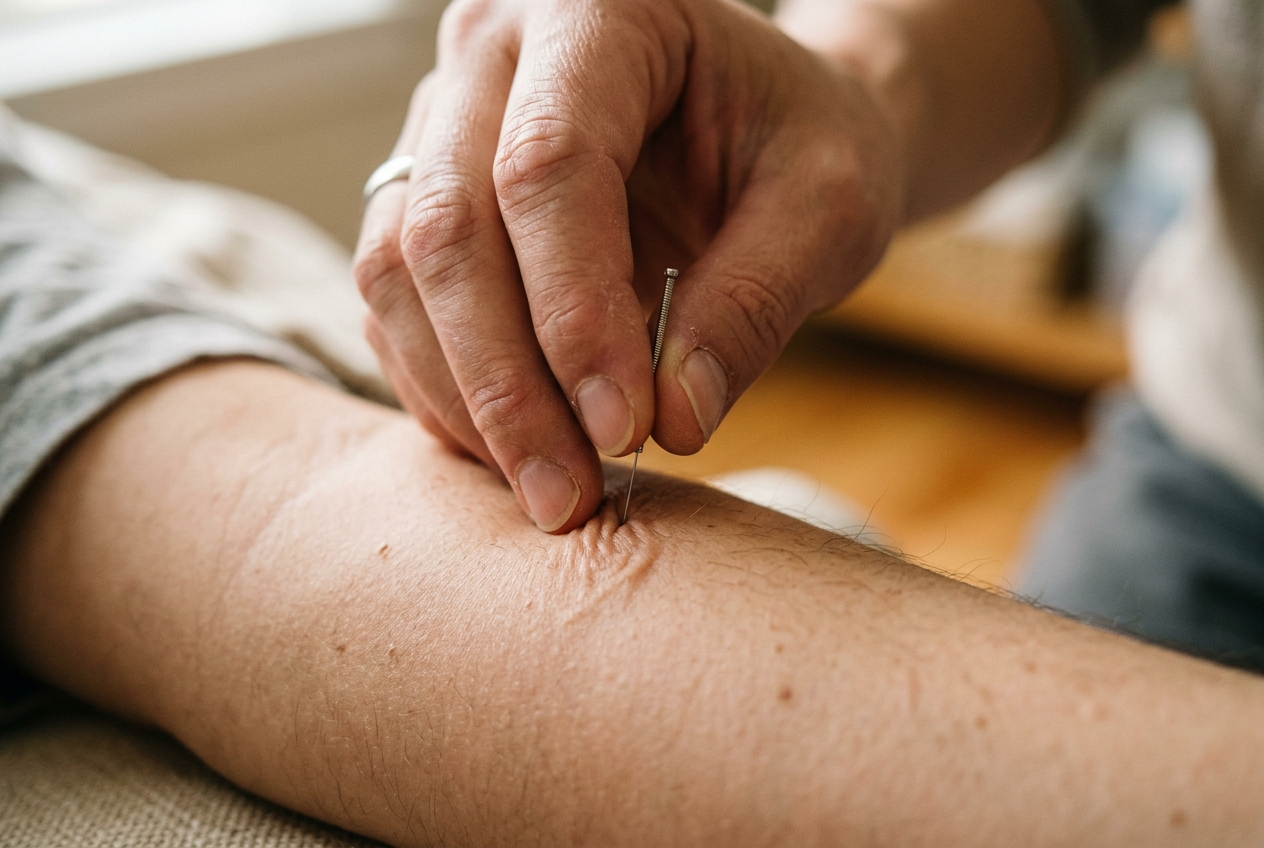
For millennia, classical Chinese medicine approached these systemic blockages not merely through chemical ingestion or broad muscular kneading, but through high-precision micro-mechanical manipulation. At the heart of this discipline lies Nian Zhuan Fa (捻转法, the Twirling-Rotating Technique)—a sophisticated rotational manipulation that applies controlled shear stress, angular displacement, and interstitial torque to acupuncture needles and manual acupressure points. Far from being an esoteric folk art, modern biomedical research demonstrates that this rotational maneuver initiates a profound cascade of cellular mechanotransduction: winding subcutaneous collagen fibers like silk around a spindle, triggering cytoskeletal remodeling in local fibroblasts, altering interstitial fluid pressure gradients, and flooding local tissue beds with analgesic extracellular adenosine.
By synthesizing the classical canonical literature—from the Han Dynasty foundational texts of the Huangdi Neijing (Yellow Emperor's Inner Canon) to the Ming Dynasty synthesis in the Zhenjiu Dacheng (Great Compendium of Acupuncture and Moxibustion)—with contemporary biomechanical and fascia research, this treatise provides an exhaustive, clinician-grade analysis of Nian Zhuan Fa. Whether deployed with a stainless-steel filiform needle or the focused vector of a trained human thumb, the physics of rotational manipulation offers a rigorous, somatic blueprint for regulating physiological homeostasis.
1. The Classical Lineage of Rotational Dynamics
The formal codification of rotational needle manipulation traces directly to the Lingshu (Spiritual Pivot) portion of the Huangdi Neijing (circa 100 BCE). In chapters such as Jiu Zhen Shi Er Yuan (Nine Needles and Twelve Yuan Sources) and Guan Zhen (Official Needling Methods), the authors established that the mere physical insertion of an instrument is clinically inert until De Qi (得气, the arrival of vital energetic resonance) is elicited. Rotational manipulation was formulated as the primary kinetic vehicle to engage, steer, and anchor this phenomenon.
During the Ming Dynasty, the master acupuncturist Yang Jizhou crystallized these manual mechanics in his encyclopedic Zhen Jiu Da Cheng (1601 CE). Yang delineated the fundamental operational parameters of Nian Zhuan Fa, formally bifurcating the technique into two opposing functional paradigms: Bu Fa (补法, Tonification or Supplementation) and Xie Fa (泻法, Sedation or Drainage).
According to classical doctrine, these paradigms are governed by four interdependent biomechanical variables:
- Angular Amplitude: The total arc of rotational displacement. Small-amplitude rotations (typically less than $90^\circ$) preserve tissue structural integrity and gently stimulate local mechanoreceptors (reinforcing the physiological baseline, or Bu). Large-amplitude rotations ($180^\circ$ to $360^\circ$) exert aggressive rotational displacement upon the surrounding fascia, mechanically unraveling stagnant bioelectric and muscular tension (Xie).
- Rotational Frequency and Cadence: The velocity of the cyclic oscillations. Tonification mandates a slow, rhythmic, and even cadence (approximately 50–60 cycles per minute), whereas Sedation employs a rapid, forceful, and irregular oscillation (exceeding 120–180 cycles per minute).
- Directional Vectoring (Zuo Zhuan vs. You Zhuan): Classical theory pairs clockwise rotation (left-turning, Zuo Zhuan, driven by forward advancement of the practitioner's thumb) with the reinforcement of Yang and channel-flow alignment (Sui, following the meridian). Conversely, counter-clockwise rotation (right-turning, You Zhuan, driven by retracting the thumb) opposes the channel trajectory (Ying, intercepting the meridian), executing clinical dispersion.
- Torque Application Regimes: Classical manipulation distinguishes between Continuous Unidirectional Torque—where the rotation is maintained predominantly in one vector with minimal counter-recoil, causing progressive fascial winding—and Intermittent Oscillating Torque, where symmetrical bidirectional twisting generates alternating elastodynamic waves through the interstitial matrix.
2. The Meridian Path: A Tangible Topography of Somatic Channels
To appreciate how rotational torque influences systemic physiology, one must discard abstract mysticism and examine the somatic terrain charted by the meridian networks. Far from arbitrary conduits, classical meridian trajectories track myofascial intermuscular septa, neurovascular bundles, and connective tissue cleavage planes.
When an acupuncturist or manual therapist palpates these channels, they are not assessing an imaginary line; they are feeling for subtle shifts in tissue compliance: taut bands, fascial densifications, temperature differentials, and neurovascular entrapment zones.
3. Connective Tissue Biophysics: The Cellular Mechanics of Torque
The physiological validation of Nian Zhuan Fa has emerged from the intersection of biomechanics, cell biology, and neurophysiology. Groundbreaking research led by Dr. Helene Langevin and published in PubMed / The Anatomical Record demonstrates that the rotational manipulation of a needle or deep manual focal pressure produces a quantifiable physical phenomenon known as helical collagen winding.
Helical Collagen Winding and Shear Strain
When a needle penetrates the subcutaneous tissue, it passes through an unorganized, compliant mesh of loose connective tissue rich in Type I and Type III collagen fibrils and elastin fibers, suspended in a hydrated glycosaminoglycan ground substance. As the rotational vector of Nian Zhuan Fa is engaged: - The superficial collagen fibers adhere mechanically to the needle surface via hydrophobic and electrostatic interactions. - Continued rotation transforms this adhesion into a mechanical wrap: the collagen fibers wind helically around the needle shaft, drawing the surrounding extracellular matrix (ECM) inward toward the center of rotation. - In manual acupressure, deep compressive rotational shear vectors mimic this process by mobilizing the superficial fascia across the deep muscular epimysium, generating localized interstitial shear strain.
Fibroblast Cytoskeletal Remodeling
This extracellular mechanical pull is directly transmitted to resident subcutaneous fibroblasts via transmembrane integrin receptors ($\alpha_1\beta_1$ and $\alpha_2\beta_1$). As detailed in PubMed / Cell Motility and the Cytoskeleton, fibroblasts respond to this mechanical strain within minutes by undergoing profound morphological alterations: - The cells flatten and extend large, lamellar cytoplasmic sheets. - Intracellular monomeric G-actin rapidly polymerizes into filamentous F-actin stress fibers. - The sustained cytoskeletal tension induces a sustained relaxation of the surrounding fascial matrix, explaining the progressive reduction in tissue stiffness following classical rotational needle retention.
Interstitial Fluid Dynamics and Hydraulic Pressure Gradients
The tight helical compaction of collagen fibrils during Nian Zhuan Fa creates an instantaneous local reduction in ECM pore volume. This mechanical compression forces interstitial fluid out of the perineedle zone, establishing a steep hydraulic pressure gradient across the fascial plane. When the rotational torque is intermittently reversed or relaxed, fluid rapidly re-enters the tissue bed. This cyclical convective flow enhances microvascular permeability, flushes accumulated inflammatory catabolites (such as substance P, bradykinin, and lactic acid), and restructures the local pericellular microenvironment.
The Purinergic Signaling Cascade: Adenosine A1 Receptor Activation
The mechanical deformation of the plasma membrane during rotational shear triggers the non-lytic exocytosis of adenosine triphosphate (ATP) into the extracellular interstitial space. As rigorously demonstrated in Nature Neuroscience / PubMed, this extracellular ATP is rapidly hydrolyzed by a cascade of membrane-bound ectonucleotidases—specifically ectonucleoside triphosphate diphosphohydrolase-1 (CD39) and ecto-5'-nucleotidase (CD73)—into adenosine.
Extracellular adenosine acts as a potent biological antinociceptive agent. By selectively binding to local Adenosine A1 receptors ($A_1R$) located on unmyelinated C-fiber and thinly myelinated A$\delta$-fiber sensory nerve terminals: - It inhibits hyperpolarization-activated cyclic nucleotide-gated channels and voltage-gated calcium channels. - It suppresses the propagation of action potentials to the dorsal horn of the spinal cord. - This purinergic cascade constitutes the primary molecular mechanism underlying the profound, long-lasting local and systemic analgesia elicited by classical Nian Zhuan Fa.
4. Master Acupressure Points: Clinical Rotational Protocols
Applying Nian Zhuan Fa in a clinical setting requires exact anatomical localization, precise depth stratification, and distinct rotational parameters tailored to each point's specific neurofascial architecture, as standardized in the World Health Organization (WHO) Standard Acupuncture Point Locations.
Point 1: LI4 (Hegu, 合谷 — "Joining Valleys")
- Everyday Landmark: Adduct your thumb tightly against the side of your index finger. Locate the highest crest of the muscular bulge that forms on the back of your hand. Relax the hand; the point lies in the depression immediately radial to the midpoint of the second metacarpal bone.
- Depth Stratification: Palpate through the skin and subcutaneous fascia into the belly of the first dorsal interosseous muscle, feeling for the firm resistance of the adductor pollicis boundary.
- Rotational Manipulation Protocol:
- Objective: Sedation and systemic pain dispersion (Xie Fa).
- Vector: Counter-clockwise rotational shear using the tip of the opposite thumb.
- Parameters: Large amplitude ($180^\circ$ to $270^\circ$), cadence of 120 oscillations per minute. Apply sustained, deep perpendicular pressure while maintaining rotational oscillation for 90 to 120 seconds.
- De Qi Somatosensory Signature: A heavy, expanding ache (Suan Zhang, 酸胀) that radiates proximally along the radial artery pathway to the wrist, frequently ascending to the ipsilateral jawline.
- Primary Clinical Indications: Tension-type and cervicogenic headaches, temporomandibular joint (TMJ) dysfunction, acute sinusitis, and systemic orofacial analgesia.
Point 2: ST36 (Zusanli, 足三里 — "Leg Three Miles")
- Everyday Landmark: Sit with the knee flexed at $90^\circ$. Locate the small depression on the outer edge of the knee just below the kneecap. Place four fingers horizontally across the upper shinbone below this hollow. ST36 is located one fingerbreadth lateral to the sharp crest of your shinbone, resting in the fleshy groove of the front leg muscle.
- Depth Stratification: Penetrate the dense crural fascia into the belly of the tibialis anterior muscle, precisely where the motor branches of the deep fibular nerve interface with the anterior tibial recurrent vessels.
- Rotational Manipulation Protocol:
- Objective: Tonification and metabolic restoration (Bu Fa).
- Vector: Clockwise rotational torque (forward thumb vector) synchronized with deep, sustained inward pressure.
- Parameters: Small-to-moderate amplitude ($60^\circ$ to $90^\circ$), slow, rhythmic cadence of 50–60 oscillations per minute for 2 to 3 minutes.
- De Qi Somatosensory Signature: A profound, warm, spreading sensation characterized by dull distension (Zhang) that travels distally down the anterior compartment of the lower leg to the dorsum of the foot, often accompanied by audible borborygmi (stomach rumbling) reflecting vagal parasympathetic activation.
- Primary Clinical Indications: Chronic physical fatigue, gastrointestinal dysmotility (gastric distension, postprandial bloating), functional dyspepsia, and generalized immune/metabolic exhaustion.
Point 3: LR3 (Taichong, 太冲 — "Great Surge")
- Everyday Landmark: Slide your finger backward along the top of your foot in the valley between your big toe and second toe. As you move upward toward your ankle, your finger will naturally drop into a distinct, sensitive depression just before the two metatarsal bones join in a "V" shape.
- Depth Stratification: Traverse the dorsal subcutaneous fascia, passing the lateral border of the extensor hallucis longus tendon to engage the interosseous connective tissue, closely adjacent to the dorsalis pedis vascular bundle and the deep peroneal nerve.
- Rotational Manipulation Protocol:
- Objective: Sedation, hepatic Qi regulation, and sympathetic suppression (Xie Fa).
- Vector: Alternating bidirectional rotational shear with emphasis on the counter-clockwise release phase.
- Parameters: Moderate-to-large amplitude ($120^\circ$ to $180^\circ$), slow, firm, and deep cadence (60–80 oscillations per minute) for 90 seconds per limb.
- De Qi Somatosensory Signature: An acute, sharp, spreading ache (Suan) that quickly gives way to a relaxing numbness, traveling proximally up the medial aspect of the leg toward the medial knee.
- Primary Clinical Indications: Sympathetic overdrive, irritability, emotional stress, hypertension, ocular strain, and vertex or temporal throbbing headaches.
Point 4: PC6 (Neiguan, 内关 — "Inner Gate")
- Everyday Landmark: Turn your hand palm-up. Lay three fingers of the opposite hand across the inside of your wrist, starting from the main wrist crease. PC6 lies precisely in the center of your forearm, three fingerbreadths above that crease, nested directly between the two prominent cord-like tendons that stand out when you make a fist.
- Depth Stratification: Positioned between the tendons of the palmaris longus and flexor carpi radialis, directly overlying the flexor digitorum superficialis and the main trunk of the median nerve.
- Rotational Manipulation Protocol:
- Objective: Harmonization, cardioprotection, and vagal down-regulation.
- Vector: Subtle, micro-amplitude rotational oscillation ($45^\circ$ to $60^\circ$).
- Parameters: Gentle, non-invasive cadence (60 oscillations per minute) coupled with steady, moderate compression for 2 minutes. Avoid aggressive drilling to prevent electrical paresthesia of the median nerve.
- De Qi Somatosensory Signature: A radiating, fine tingling or gentle warm sensation traveling along the palmar aspect of the arm up to the cubital fossa and into the anterior precordial chest wall.
- Primary Clinical Indications: Psychogenic nausea, motion sickness, epigastric tightness, palpitations, anxiety-induced tachycardia, and insomnia.
5. Comparative Synergy: Nian Zhuan Fa and Axial Ti Cha Fa
In classical clinical practice, Nian Zhuan Fa is rarely executed in complete isolation. Instead, it operates in dynamic biomechanical synergy with Ti Cha Fa (提插法, the Lifting-Thrusting Technique)—the axial translation of mechanical force along the vertical axis of the point.
The functional integration of these two manipulation techniques alters the physical response of the target tissue: - Axial Ti Cha Fa provides broad perpendicular recruitment across fascial layers (from superficial fascia to deep epimysium), creating vertical piston forces that alter hydrostatic tissue pressure. - Rotational Nian Zhuan Fa captures and binds the horizontal transverse fibers within that layer, anchoring the tissue to the mechanical source. - When applied in sequence—first anchoring the tissue with a $180^\circ$ Nian Zhuan rotation, followed by short, rapid Ti Cha axial micro-thrusts—the localized strain field is magnified by up to 300% compared to linear displacement alone, eliciting immediate, robust De Qi.
6. Comprehensive Protocol: The Evening Neurovegetative Reset
To demonstrate the real-world clinical application of rotational mechanics, consider a common modern clinical presentation: The Sympathetic Overdrive Syndrome.
Clinical Scenario
A patient presents at 8:00 PM following an intense 10-hour day of computational work. Key somatic findings: - Severe suboccipital and temporal tension headache. - Clenched jaw (bruxism) and tight upper trapezius bands. - Postprandial epigastric distension and slow digestion. - Generalized nervous agitation, hyper-alert autonomic state, and difficulty falling asleep.
The "Four Gates" + Neuro-Enteric Axis Protocol
This protocol combines the classical bilateral "Four Gates" (Si Guan, 四关: LI4 + LR3) with PC6 and ST36 to re-establish the balance between the sympathetic and parasympathetic nervous systems.
7. Safety, Clinical Precautions, and Practical Sense
While manual acupressure and rotational manipulation are non-pharmacological and exceptionally safe when applied correctly, practitioners and patients must understand its clear physiological boundaries.
8. Today's Takeaway: The Two-Minute Desk Reset
You do not need to wait for a scheduled clinical appointment to experience the tangible mechanotransductive effects of Nian Zhuan Fa. If you are feeling screen-fatigued, mentally overstimulated, or neck-strained right now, execute this two-minute micro-protocol before moving forward.
By understanding Nian Zhuan Fa as an applied science—where classical rotational maneuvers directly engage the living matrix of collagen, fibroblasts, and purinergic receptors—we bridge the gap between ancient clinical intuition and modern biophysical medicine. The body is not a machine of isolated parts, but an interconnected, responsive network waiting for the right mechanical key.
Authoritative Scientific & Clinical References
- Langevin, H. M., et al. (2001). Mechanical significance of acupuncture needle manipulation. PubMed: The Anatomical Record.
- Langevin, H. M., et al. (2002). Subcutaneous tissue fibroblast cytoskeletal remodeling induced by acupuncture. PubMed: Cell Motility and the Cytoskeleton.
- Goldman, N., et al. (2010). Adenosine A1 receptors mediate local anti-nociceptive effects of acupuncture. PubMed: Nature Neuroscience.
- World Health Organization. Standard Acupuncture Point Locations in the Western Pacific Region. WHO IRIS Repository / Guidelines.
- Yang Jizhou (Ming Dynasty). Zhen Jiu Da Cheng (Compendium of Acupuncture and Moxibustion). Historical Archive / Overview.