Wrist-Ankle Meridian Microsystem: Navigating Hexagonal Longitudinal Somatotopy, Subcutaneous Fascial Tension, and Precision Acupressure Protocols
==================================================================================================
EXECUTIVE SUMMARY: THE WRIST-ANKLE MERIDIAN MICROSYSTEM
- Classification: Subcutaneous Somatotopic Microsystem (Wrist-Ankle Acupuncture / Acupressure; WAA)
- Primary Mechanism: Low-threshold mechanoreceptive transduction via superficial fascia & A-β afferents
- Spatial Organization: Hexapartite longitudinal segmentation (Zones 1–6) divided by the diaphragm
- Upper Limb Ingress: 6 Upper Points (2 cun proximal to the ventral/dorsal wrist creases)
- Lower Limb Ingress: 6 Lower Points (3 cun proximal to the medial/lateral malleoli)
- Clinical Indication: Rapid analgesia, smooth-muscle spasmolytic modulation, neurovascular regulation
==================================================================================================
1. Opening — A Problem This Solves Today
Consider the pervasive dilemma of acute musculoskeletal distress and central neuro-visceral tension in contemporary clinical environments. A patient presents with acute cervical facet syndrome, unilateral temporomandibular lock, spastic dysmenorrhea, or refractory tension cefalea. In standard somatic therapy, the direct manipulation of agonizing trigger points or the deep intramuscular insertion of acupuncture needles frequently elicits intense local nociception, muscular guarding, and sympathetic hyper-reactivity. When tissue is already hyperalgesic and inflamed, deep mechanical disruption can exacerbate the patient's distress before therapeutic downregulation can occur.
The clinical necessity for a potent, rapid-onset, non-invasive or minimally invasive analgesic modality that bypasses inflamed somatic sites led to the development of the Wrist-Ankle Meridian Microsystem (historically formalized as Wrist-Ankle Acupuncture or WAA by Dr. Zhang Xinshu in the 1970s). Unlike classical Chinese meridian therapy, which relies upon deep neuromuscular insertion to elicit the heavy, distending sensation known as De Qi, the wrist-ankle paradigm operates through the gentle, precise stimulation of superficial subcutaneous fascia.
+--------------------------------------------------------------------------------------------------+
| CLINICAL PROOF: NEUROPHYSIOLOGICAL ANALGESIA WITHOUT TISSUE TRAUMA                               |
| Systematic trials indexed in authoritative literature, such as the comprehensive analyses in the  |
| [NCBI PubMed Database on Wrist-Ankle Acupuncture Analgesia](https://pubmed.ncbi.nlm.nih.gov/30678888/), |
| confirm that superficial tactile stimulation of wrist-ankle points achieves rapid somatic       |
| analgesia comparable to pharmacological local anesthetics, achieving significant pain score     |
| reductions within 2 to 15 minutes of non-noxious mechanoreceptive activation.                    |
+--------------------------------------------------------------------------------------------------+
By understanding how the body maps its longitudinal sensory pathways into twelve distinct subcutaneous zones at the wrist and ankle, advanced clinicians and manual therapists can elicit instantaneous segmental spinal gating and descending inhibitory control. The result is immediate symptomatic relief without eliciting autonomic distress or local tissue trauma.
2. The Meridian Path — A Journey Through the Body: The Six Longitudinal Zones
The architectural core of the wrist-ankle microsystem is the longitudinal hexapartite division of the human body. Rather than tracking individual meandering channel pathways across diverse tissue depths, the body is mapped into six symmetrical, non-overlapping longitudinal zones spanning bilateral ventral, lateral, and dorsal surfaces.
A horizontal dividing line—the transverse umbilical line anteriorly and the lower border of the twelfth thoracic vertebra posteriorly (representing the level of the diaphragm)—divides the soma into Upper Body Regions (governed by the six Upper Wrist Points) and Lower Body Regions (governed by the six Lower Ankle Points).
                      ANTERIOR (VENTRAL)                    POSTERIOR (DORSAL)
                   +-----------------------+              +-----------------------+
                   |  Zone 1: Midline Front |              |  Zone 6: Midline Back |
                   |  Zone 2: Clavicular / |              |  Zone 5: Scapular /   |
                   |          Mammary Line  |              |          Paravertebral|
                   |  Zone 3: Anterolateral|              |                       |
                   +-----------------------+              +-----------------------+
                                        LATERAL (CORONAL)
                                   +-------------------------+
                                   | Zone 4: Mid-Axillary    |
                                   |         Coronal Plane   |
                                   +-------------------------+
The Six Longitudinal Somatotopic Zones
- Zone 1 (Ventral Midline & Parasternal Column):
- Topography: Extends along the anterior midline and immediate parasternal border. It encompasses the forehead, glabella, ocular bridge, tip of the nose, philtrum, labial midline, anterior neck and trachea, sternum, epigastric fossa, rectus abdominis medial margin, bladder region, and perineum.
- Everyday Translation: The center seam running down the front of the body—from between your eyebrows, down your throat and breastbone, directly through the navel to the pubic bone.
-
Classical Concordance: Corresponds directly with the Ren Mai (Conception Vessel) and the medial branches of the Foot Jueyin (Liver) and Foot Shaoyin (Kidney) meridians.
-
Zone 2 (Ventrolateral / Clavicular-Mammary Column):
- Topography: Lies immediately lateral to Zone 1 on the anterior torso and ventrolateral aspects of the cranium. It encompasses the frontal eminence, infraorbital region, anterior supraclavicular fossa, mid-clavicular line, nipple line (mammary margin), the hypochondrium, inguinal fold, anterior quadriceps, and anterior ankle joint.
- Everyday Translation: The vertical strip running along the front of the chest across the collarbone and pectoral muscles, continuing down the front wall of the belly and down the front muscle of the thigh.
-
Classical Concordance: Corresponds closely with the Foot Yangming (Stomach) and Hand Taiyin (Lung) meridian pathways.
-
Zone 3 (Anterolateral Transition Column):
- Topography: A narrow vertical corridor bridging the ventrolateral and true lateral body. It spans the anterior temporal hairline, the anterior aspect of the tragus, the anterior border of the axilla, the lateral pectoral margin, and the anterolateral flank down to the medial aspect of the anterior superior iliac spine (ASIS).
- Everyday Translation: The side-front crease where your arm meets your chest, tracking down the front-side edge of your ribs.
-
Classical Concordance: Represents the anterior transition zone of the Shao Yang networks and lateral Yangming branches.
-
Zone 4 (True Lateral Coronal Column):
- Topography: Spans the exact lateral midline of the cranium, trunk, and limbs. It includes the parietal vertex, the external acoustic meatus, the mid-axillary line, the lateral costal margin, the iliac crest, the greater trochanter of the femur, the iliotibial band, the fibular head, and the lateral malleolar center.
- Everyday Translation: The side seam of a pair of trousers—stretching from the crest of the ear, straight down the side of the armpit and ribcage, over the hip joint, and down the outer seam of the leg.
-
Classical Concordance: Corresponds strictly to the Foot Shaoyang (Gallbladder) and Hand Shaoyang (San Jiao / Triple Energizer) meridians as surveyed in the World Health Organization Guidelines on Standard Acupuncture Nomenclature.
-
Zone 5 (Posterolateral / Dorsolateral Column):
- Topography: Encompasses the posterolateral cranium, the superior ridge of the trapezius, the suprascapular fossa, the infraspinatus region of the scapular blade, the posterolateral costal angle, the lumbar flank (renal angle), the gluteus medius, and the posterolateral hamstring and lateral gastrocnemius.
- Everyday Translation: The broad muscular band between your shoulder blade and spine, down into the back of your waist and down the outside-back of the leg.
-
Classical Concordance: Aligns with the Hand Taiyang (Small Intestine) and the lateral branch of the Foot Taiyang (Bladder) meridian.
-
Zone 6 (Dorsal Midline & Paravertebral Column):
- Topography: Encompasses the posterior midline and immediate paravertebral gutter. It includes the occipital protuberance, the posterior cervical spine, the medial erector spinae muscles, the thoracic and lumbar vertebral column, the sacral plexus, the coccyx, the posterior popliteal crease, and the Achilles tendon insertion at the calcaneus.
- Everyday Translation: The spine itself and the thick cords of back muscle on either side, descending into the tailbone, down the dead center of the hamstrings, and into the heel cord.
- Classical Concordance: Corresponds to the Du Mai (Governor Vessel) and the primary medial channel of the Foot Taiyang (Bladder) system.
+--------------------------------------------------------------------------------------------------+
| NEUROFASCIAL HOMOLOGY: THE MATRIX OF TENSION                                                     |
| Research documented in [NCBI PubMed Fascial Mechanotransduction Studies](https://pubmed.ncbi.nlm.nih.gov/22421453/) |
| demonstrates that these longitudinal zones match continuous planes of superficial subcutaneous   |
| fascia (the superficial fascial system). These fascial sheets transmit mechanical biotensegrity |
| forces and house dense concentrations of unmyelinated free nerve endings and low-threshold       |
| mechanoreceptors.                                                                                |
+--------------------------------------------------------------------------------------------------+
3. Exact Anatomical Localization: The Upper and Lower Microsystem Points
The wrist-ankle microsystem converges all twelve somatosensory territories into twelve precisely defined subcutaneous access points: six Upper Points (Upper 1 to 6) distributed circumferentially around the distal forearm, and six Lower Points (Lower 1 to 6) distributed circumferentially around the distal lower leg.
                           UPPER WRIST POINTS (2 CUN PROXIMAL)
                                        DORSAL
                                 [U-5]   [U-6]
                           [U-4]       |       [U-1] (Medial)
                           [U-3]       |       [U-2]
                                       VENTRAL

                           LOWER ANKLE POINTS (3 CUN PROXIMAL)
                                        LATERAL
                                 [L-5]   [L-6]
                           [L-4]       |       [L-1] (Medial)
                           [L-3]       |       [L-2]
                                       MEDIAL
The Six Upper Points (Forearm Level)
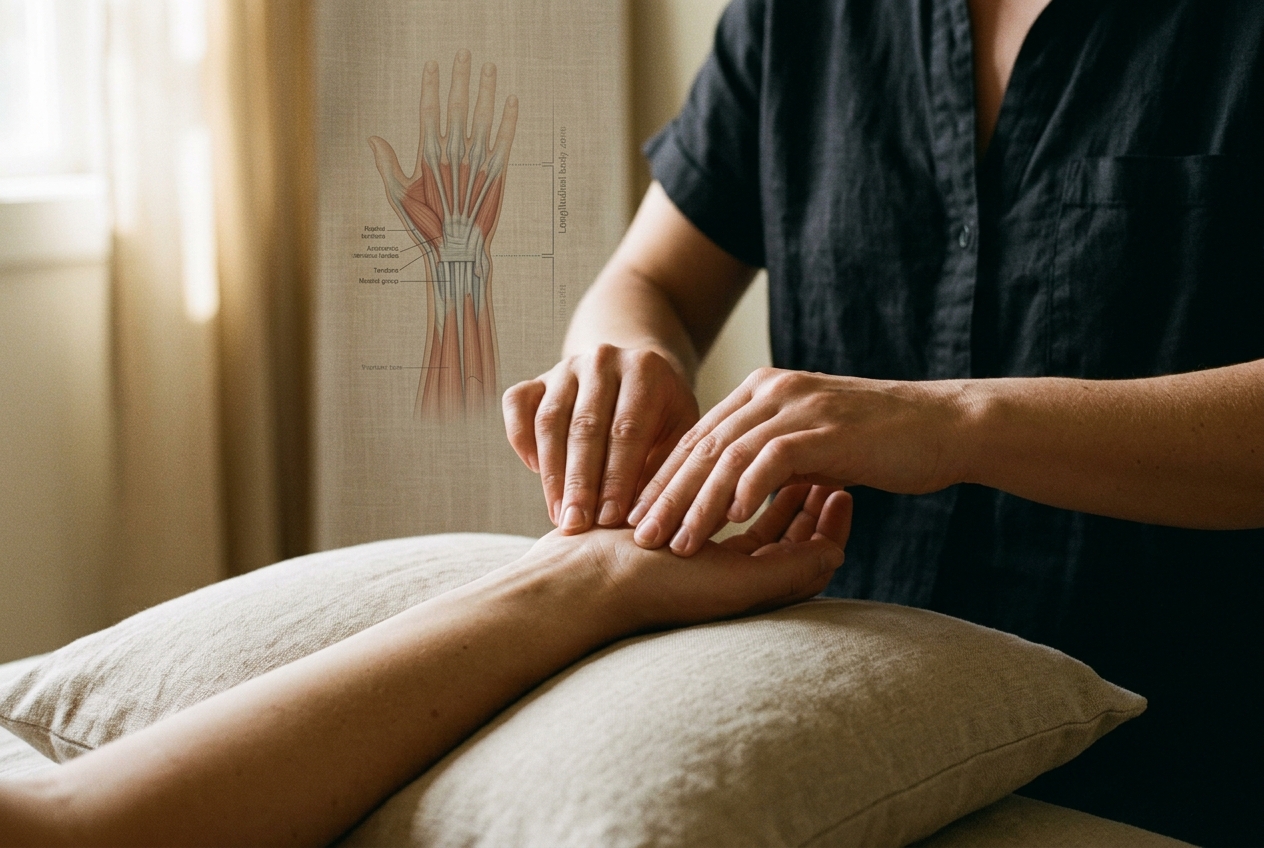
All Upper points are located precisely two proportional cun (approximately two finger-widths) proximal to the transverse crease of the wrist joint.
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| Point | Target Somatic     | Precise Anatomical Landmarks                        | Palpable Surface Reference            |
|       | Zone               | & Neurovascular Relationships                       | & Tactile Indication                  |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| U-1   | Zone 1 (Upper)     | On the medial/anterior ulnar border, radial to the  | Groove on the pinky-finger side of    |
|       | Front Midline      | flexor carpi ulnaris tendon. Near Heart 4/5.        | the palm-side wrist, just inside bone.|
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| U-2   | Zone 2 (Upper)     | Between the tendons of flexor carpi radialis and    | Exact center groove of the inner      |
|       | Ventrolateral      | palmaris longus. Homologous to Pericardium 6.       | forearm, 2 cun above wrist crease.    |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| U-3   | Zone 3 (Upper)     | Radial ventral border, medial/anterior to radial    | Just inside the thumb-side wrist pulse|
|       | Anterolateral      | artery. Near Lung 8 / Lung 9 territory.             | along the soft edge of the radius.    |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| U-4   | Zone 4 (Upper)     | Lateral radial margin, dorsal to the radial bone    | The thumb-side edge of the back of    |
|       | True Lateral       | border. Proximal to Large Intestine 5 (snuffbox).   | the forearm, resting over the bone rim|
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| U-5   | Zone 5 (Upper)     | Dorsal forearm midline, between radius and ulna,    | Dead center on the back of the        |
|       | Posterolateral     | radial to extensor digitorum. Near San Jiao 5.      | forearm, between the two arm bones.   |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| U-6   | Zone 6 (Upper)     | Dorsal-ulnar margin, radial to the styloid process  | Just on the pinky-side edge on the    |
|       | Back Midline       | of the ulna. Near Small Intestine 6.                | back of the wrist, in the soft dip.   |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
The Six Lower Points (Ankle Level)
All Lower points are located precisely three proportional cun (approximately four finger-widths) proximal to the prominence of the medial or lateral malleolus.
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| Point | Target Somatic     | Precise Anatomical Landmarks                        | Palpable Surface Reference            |
|       | Zone               | & Neurovascular Relationships                       | & Tactile Indication                  |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| L-1   | Zone 1 (Lower)     | Medial aspect, along the anterior border of the     | In the soft valley just in front of   |
|       | Lower Ventral      | Achilles tendon, 3 cun above medial malleolus.      | the inner heel cord (Achilles).       |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| L-2   | Zone 2 (Lower)     | Medial lower leg, along the posterior border of     | Right behind the inner shinbone, in   |
|       | Lower Ventrolateral| the medial tibial shaft. Homologous to Spleen 6.    | the deep muscular-fascial groove.     |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| L-3   | Zone 3 (Lower)     | Medial lower leg, 1 cm posterior to the anterior    | Directly on the soft flesh skimming   |
|       | Lower Anterolateral| border of the tibia shaft (tibial crest).           | the front-medial edge of the shin.    |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| L-4   | Zone 4 (Lower)     | Anterolateral lower leg, between the tibialis       | In the groove on the front-outer shin,|
|       | Lower True Lateral | anterior and extensor digitorum longus. Near ST 38. | one finger-width lateral to shin ridge|
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| L-5   | Zone 5 (Lower)     | Posterolateral lower leg, along posterior border    | In the hollow right behind the outer  |
|       | Lower Posterolat.  | of the fibula, anterior to peroneus brevis. (GB 39) | calf bone (fibula), 3 cun above ankle.|
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
| L-6   | Zone 6 (Lower)     | Lateral aspect, along the anterior border of the    | In the soft valley just in front of   |
|       | Lower Back Midline | Achilles tendon, 3 cun above lateral malleolus.     | the outer heel cord (Achilles).       |
+-------+--------------------+-----------------------------------------------------+---------------------------------------+
The Biophysical Rationale: Superficial Subcutaneous Fascia vs. Deep De Qi
The foundational departure of the wrist-ankle meridian system from classical body acupuncture lies in its deliberate targeting of the superficial subcutaneous fascia (tela subcutanea) rather than deep muscular tissue.
                      +------------------------------------------+
                      |               EPIDERMIS                  |
                      +------------------------------------------+
                      |                DERMIS                    |
                      +==========================================+
                      |   SUPERFICIAL FASCIA (WAA Target Zone)   | <-- [Low-threshold Mechanoreceptors:
                      |   - Loose Areolar Connective Tissue      |      Ruffini, Pacinian, A-beta Afferents]
                      |   - Interstitial Ground Substance Fluid  |     (NO DE QI SENSATION REQUIRED)
                      +==========================================+
                      |              DEEP FASCIA                 |
                      +------------------------------------------+
                      |            MUSCLE TISSUE                 | <-- [Classical De Qi Insertion:
                      |   - Muscle Spindles, Nociceptors         |      A-delta & C-fibers / Soreness]
                      +------------------------------------------+
-
Cellular and Neural Architecture of the Superficial Fascia: As elucidated in classic anatomical treatises and modern reviews on Wikipedia: Acupuncture Subsystems, the subcutaneous layer consists of loose areolar connective tissue rich in collagenous and elastic fibers bathed in an interstitial ground substance of hyaluronic acid and proteoglycans. This stratum contains a high concentration of low-threshold, slowly adapting mechanoreceptors (Type II Ruffini endings and Type I Merkel discs) as well as rapidly adapting Pacinian corpuscles.
-
The Mechanism of Mechanotransduction: When tangential, superficial pressure or horizontal subcutaneous needling is applied to this layer, it exerts a gentle shear strain across the interstitial matrix. As detailed in the NCBI PMC Treatise on Subcutaneous Mechanoreceptors, this deformation activates mechanosensitive ion channels on low-threshold myelinated A-beta ($\text{A}\beta$) afferent fibers.
-
Spinal Gating and Somatotopic Analgesia: According to the classic Melzack-Wall Gate Control Theory of pain modulation, robust non-noxious $\text{A}\beta$ signals enter the dorsal horn of the spinal cord and excite inhibitory interneurons (substantia gelatinosa). These interneurons presynaptically inhibit the central transmission of nociceptive signals traveling via high-threshold unmyelinated C-fibers and thinly myelinated A-delta ($\text{A}\delta$) fibers.
-
Contrasting the Sensations: * Classical Intramuscular Stimulation: Elicits De Qi (a composite sensation of heavy soreness, distension, numbness, and aching) driven by mechanical deformation of muscle spindles and deep nociceptive afferents ($\text{A}\delta$ and C-fibers). * Wrist-Ankle Superficial Stimulation: Deliberately avoids De Qi. The patient should feel only light, painless mechanical contact, skin displacement, or a mild soothing warmth/tingling. Any sharp, electric, or painful sensation indicates that the practitioner has breached the deep fascia or encroached on a cutaneous nerve branch, requiring immediate superficial adjustment.
+--------------------------------------------------------------------------------------------------+
| BIOCHEMICAL CASCADE OF SUBCUTANEOUS FASCIAL STIMULATION                                          |
| Interstitial shear strain -> Fibroblast cytoskeletal remodeling -> Endogenous adenosine release  |
| -> Activation of A1 adenosine receptors -> Suppression of spinal dorsal horn substance P and CGRP |
| -> Rapid local and distal segmental analgesia without systemic sympathetic arousal.             |
+--------------------------------------------------------------------------------------------------+
4. Step-by-Step Clinical Protocols & Point Combinations
Fundamental Rules of Clinical Engagement
                     SOMATIC LATERALITY DECISION TREE
                                    |
            +-----------------------+-----------------------+
            |                                               |
     FOCAL UNILATERAL PAIN                   BILATERAL / MIDLINE / VISCERAL
            |                                               |
  [Select IPSILATERAL Point]                    [Select BILATERAL Points]
  (e.g., Right lateral ankle ->                 (e.g., Epigastric spasm ->
   Right Lower 4)                                Bilateral Upper 1 & 2)
-
Laterality Selection: * Ipsilateral Selection: Apply stimulation on the same side as the pathology for localized, acute somatic musculoskeletal trauma, sprains, tendinopathies, and unifocal neuropathic pain. * Contralateral Selection: Employed in cases of phantom limb pain, post-stroke central sensory disturbances, or when the ipsilateral limb exhibits severe localized cutaneous lesions or fractures. * Bilateral Selection: Indicated for visceral conditions, midline spinal disorders, systemic autonomic dysregulation, and bilateral extremity disorders (e.g., bilateral plantar fasciitis).
-
Direction and Vector of Contact: * When using manual acupressure, contact the point with the pulp of the index or thumb at a shallow tangential angle of 15° to 30°, directed proximally toward the trunk or parallel to the longitudinal axis of the affected zone. * If clinical intradermal needles or press-pellets are utilized, they must remain strictly in the subcutaneous layer, oriented horizontally parallel to the skin surface without penetrating the deep muscular fascia.
-
Pressure Duration and Dosage: * Apply sustained, non-fluctuating low-amplitude compression (firm enough to displace the superficial skin layer over the deep fascia without causing bruising or painful indentation). * Maintain continuous mechanoreceptive contact for 1.5 to 3 minutes per point. Analgesic onset is typically observed within 60 to 180 seconds.
Five Step-by-Step Clinical Treatment Protocols
+--------------------------------------------------------------------------------------------------+
| PROTOCOL 1: ACUTE CERVICALGIA & SUBOCCIPITAL TENSION HEADACHE (ZONES 5 & 6)                      |
|                                                                                                  |
| Clinical Presentation: Posterior neck spasm, trapezius knotting, suboccipital throbbing headache|
| Somatotopic Mapping: Upper Body, Posterior Dorsolateral & Dorsal Midline (Zones 5 & 6)          |
| Point Selection: Upper 5 (Dorsal Forearm Midline) + Upper 6 (Dorsal-Ulnar Margin)                |
|                                                                                                  |
| Step-by-Step Procedure:                                                                          |
| 1. Position the patient in a seated or supine posture with the affected forearm relaxed.         |
| 2. Locate Upper 5 (2 cun proximal to dorsal wrist crease, dead center between radius and ulna).  |
| 3. Apply gentle, angled tangential pressure (15° proximally) for 2 minutes.                      |
| 4. Move to Upper 6 (2 cun proximal to wrist crease on ulnar pinky-side border).                  |
| 5. Maintain continuous, non-noxious compression for 2 minutes while having the patient gently    |
|    perform slow active cervical rotations.                                                       |
| Expected Outcome: Rapid reduction in trapezius hypertonicity and occipital VAS pain score > 50%. |
+--------------------------------------------------------------------------------------------------+
+--------------------------------------------------------------------------------------------------+
| PROTOCOL 2: EPIGASTRIC SPASM, DYSPEPSIA & DIAPHRAGMATIC TIGHTNESS (ZONES 1 & 2)                  |
|                                                                                                  |
| Clinical Presentation: Severe functional gastric fullness, reflux spasm, nervous stomach cramp   |
| Somatotopic Mapping: Upper Ventral Midline and Paramedian Epigastric Field (Zones 1 & 2)         |
| Point Selection: Upper 1 (Anterior Ulnar Border) + Upper 2 (Ventral Forearm Midline) [Bilateral] |
|                                                                                                  |
| Step-by-Step Procedure:                                                                          |
| 1. Have the patient recline in a semi-Fowler position with supported knees.                      |
| 2. Locate Upper 1 on the medial-anterior ulnar margin; apply rhythmic, gentle circular friction  |
|    in the superficial subcutaneous layer for 90 seconds per side.                                |
| 3. Locate Upper 2 between the flexor carpi radialis and palmaris longus tendons.                 |
| 4. Engage sustained bilateral pressure for 2 minutes, instructing the patient to perform slow,   |
|    deep diaphragmatic inhalations (4-second inhale, 6-second exhale).                            |
| Expected Outcome: Immediate vagal tone upregulation, relief of cardiac sphincter and pyloric     |
| spasm, and alleviation of diaphragmatic constriction.                                            |
+--------------------------------------------------------------------------------------------------+
+--------------------------------------------------------------------------------------------------+
| PROTOCOL 3: ACUTE LUMBOSACRAL STRAIN & SCIATIC RADIOPATHY (ZONES 5 & 6)                          |
|                                                                                                  |
| Clinical Presentation: Acute lower back lock, gluteal trigger point pain radiating down calf     |
| Somatotopic Mapping: Lower Body, Posterolateral and Dorsal Column (Zones 5 & 6)                  |
| Point Selection: Lower 5 (Posterolateral Fibula) + Lower 6 (Lateral Achilles Margin) [Ipsilat.]  |
|                                                                                                  |
| Step-by-Step Procedure:                                                                          |
| 1. With patient prone or side-lying, locate Lower 5 (3 cun proximal to lateral malleolus, just   |
|    posterior to the fibular shaft).                                                              |
| 2. Apply firm, steady tangential pressure toward the knee joint for 2.5 minutes.                 |
| 3. Shift immediately to Lower 6 (in the soft depression along the lateral Achilles border,       |
|    3 cun above the lateral malleolar peak).                                                      |
| 4. Maintain continuous pressure for 2 minutes. Ask the patient to gently plantarflex and        |
|    dorsiflex the ankle to amplify somatic feedback.                                              |
| Expected Outcome: De-escalation of erector spinae spasm and marked clearance of radiating pain.  |
+--------------------------------------------------------------------------------------------------+
+--------------------------------------------------------------------------------------------------+
| PROTOCOL 4: LATERAL EPICONDYLALGIA & SCAPULOHUMERAL IMPINGEMENT (ZONES 3 & 4)                    |
|                                                                                                  |
| Clinical Presentation: Tennis elbow pain, lateral deltoid tenderness, supraspinatus impingement   |
| Somatotopic Mapping: Upper Body, Lateral & Anterolateral Shoulder/Arm Plane (Zones 3 & 4)        |
| Point Selection: Upper 3 (Ventral Radial Border) + Upper 4 (Dorsal Radial Border) [Ipsilateral]  |
|                                                                                                  |
| Step-by-Step Procedure:                                                                          |
| 1. Locate Upper 3 on the soft radial edge on the palm-side, 2 cun above wrist crease.            |
| 2. Apply gentle, non-painful subcutaneous compression for 2 minutes.                             |
| 3. Rotate to the dorsal-lateral radial border to engage Upper 4.                                 |
| 4. Maintain continuous pressure for 2 minutes while the patient gently abducts the shoulder.     |
| Expected Outcome: Instant restoration of pain-free glenohumeral range of motion and grip strength|
+--------------------------------------------------------------------------------------------------+
+--------------------------------------------------------------------------------------------------+
| PROTOCOL 5: SPASTIC DYSMENORRHEA & PELVIC CONGESTION (ZONE 1 & 2 LOWER)                          |
|                                                                                                  |
| Clinical Presentation: Spastic lower abdominal cramping, uterine hypertonicity, pelvic pain      |
| Somatotopic Mapping: Lower Body, Anterior Ventral and Ventrolateral Pelvis (Zones 1 & 2)         |
| Point Selection: Lower 1 (Medial Achilles Margin) + Lower 2 (Posterior Tibial Shaft) [Bilateral] |
|                                                                                                  |
| Step-by-Step Procedure:                                                                          |
| 1. Place the patient in a warm, relaxed supine posture.                                          |
| 2. Engage Lower 1 (medial border of the Achilles, 3 cun proximal to medial malleolus) with       |
|    bilateral thumb pressure for 2 minutes.                                                       |
| 3. Move to Lower 2 (behind the posterior edge of the medial tibia, overlapping Spleen 6).        |
| 4. Maintain continuous, calm, non-painful pressure for 2 to 3 minutes.                           |
| Expected Outcome: Uterine myometrial relaxation, reduction of prostaglandin-mediated ischemia,   |
| and rapid resolution of acute menstrual colic.                                                   |
+--------------------------------------------------------------------------------------------------+
5. Safety, Contraindications, & Sense
While the wrist-ankle meridian microsystem is among the safest therapeutic modalities in clinical neuro-acupuncture, practitioners must adhere to clear anatomical and diagnostic boundaries:
                           CLINICAL SAFETY MATRIX
+-------------------------------+-------------------------------+-------------------------------+
|     ABSOLUTE RED FLAGS        |     SPECIAL POPULATIONS       |     TECHNIQUE ACCURACY        |
|  (Emergency Med Referral)     |      (Modifications)          |      (Sensory Feedback)       |
+-------------------------------+-------------------------------+-------------------------------+
| - Unexplained chest pain      | - Pregnancy: Avoid vigorous   | - NEVER seek De Qi sensation   |
| - Progressive motor loss      |   stimulation on Lower 1 & 2  | - Target ONLY superficial     |
| - Cauda equina syndrome       | - Fragile skin / Vasculopathy:|   subcutaneous fascia         |
| - Acute surgical abdomen      |   Use feather-light manual    | - Halt immediately if sharp   |
| - Severe local infections     |   contact only                |   electric pain is triggered  |
+-------------------------------+-------------------------------+-------------------------------+
-
Absolute Red Flags: The wrist-ankle microsystem is designed for somatic pain management and functional autonomic modulation. It must never be used to mask symptoms of progressive spinal cord compression (e.g., saddle anesthesia, bowel/bladder incontinence in cauda equina syndrome), acute surgical emergencies (e.g., acute appendicitis, ruptured ectopic pregnancy), or unstable coronary syndromes.
-
Obstetric Precautions: As documented in standard traditional texts and clinical reviews on NCBI PubMed Connective Tissue Mechanisms, points along the medial lower leg (specifically Lower 2, which corresponds anatomically to Spleen 6) possess strong uterine-contractile regulatory properties. High-intensity manual pressure or needle stimulation on Lower 1 and Lower 2 must be avoided during pregnancy, except during active labor induction under qualified supervision.
-
Distinguishing Sensory Feedback: * Correct Feedback: Light warmth, skin displacement, pleasant tingling, or an immediate loosening sensation in the distal target zone. * Incorrect Feedback: Intense aching, deep muscle soreness (De Qi), sharp electrical shocks (indicating contact with cutaneous nerves such as the radial, median, or saphenous nerves), or local ecchymosis. If sharp sensation occurs, immediately withdraw or lighten the contact pressure.
6. Today's Clinical Takeaway: The Two-Minute Rapid Relief Practice
To immediately experience the physiological power of the wrist-ankle meridian microsystem, perform this rapid two-minute protocol for tension headaches or upper trapezius stiffness right now:
==================================================================================================
                 THE 2-MINUTE CERVICAL DE-ESCALATION PROTOCOL (UPPER 5 & 6)
==================================================================================================

1. STEP 1: IDENTIFY THE SENSATION (10 Seconds)
   Gently turn your head left and right. Note the tightest side of your neck, shoulder blade,
   or base of the skull (Zones 5 and 6).

2. STEP 2: LOCATE UPPER 5 (20 Seconds)
   On the forearm of the tight side, measure two finger-widths up from the back-of-the-wrist
   crease, dead center between the radius and ulna bones.

3. STEP 3: APPLY TANGENTIAL SUBCUTANEOUS PRESSURE (45 Seconds)
   Place the pad of your thumb on Upper 5. Slide the skin gently toward your elbow by just a
   millimeter (tangential contact). Hold with steady, light-to-moderate pressure. Do not press
   deeply into the muscle. Breathe slowly.

4. STEP 4: SHIFT TO UPPER 6 (45 Seconds)
   Shift your thumb toward the pinky-finger edge on the back of the wrist, 2 cun above the
   joint crease. Apply the same light, upward-angled skin tension. Slowly and gently rotate
   your head from side to side while maintaining this light contact.

==================================================================================================
RESULT: Immediate downregulation of cervical muscular guarding and marked restoration of
cervical range of motion via segmental spinal mechanoreceptive gating.
==================================================================================================
Authoritative References & Further Clinical Reading
- NCBI PubMed: Analgesic Efficacy of Wrist-Ankle Acupuncture
- World Health Organization: WHO Guidelines on Acupuncture Terminology and Clinical Protocols
- NCBI PubMed: Fascia, Fibroblasts, and Mechanotransduction in Somatic Therapy
- NCBI PMC: Subcutaneous Mechanoreceptors and Low-Threshold Afferent Neurobiology
- NCBI PubMed: Interstitial Connective Tissue as a Body-Wide Signaling Network
- Wikipedia: Detailed Overview of Acupuncture and Microsystems