Mu-Shu Point Combination: Navigating Ventral-Dorsal Visceral Synergy, Yin-Yang Channel Regulation, and Paired Acupressure Protocols
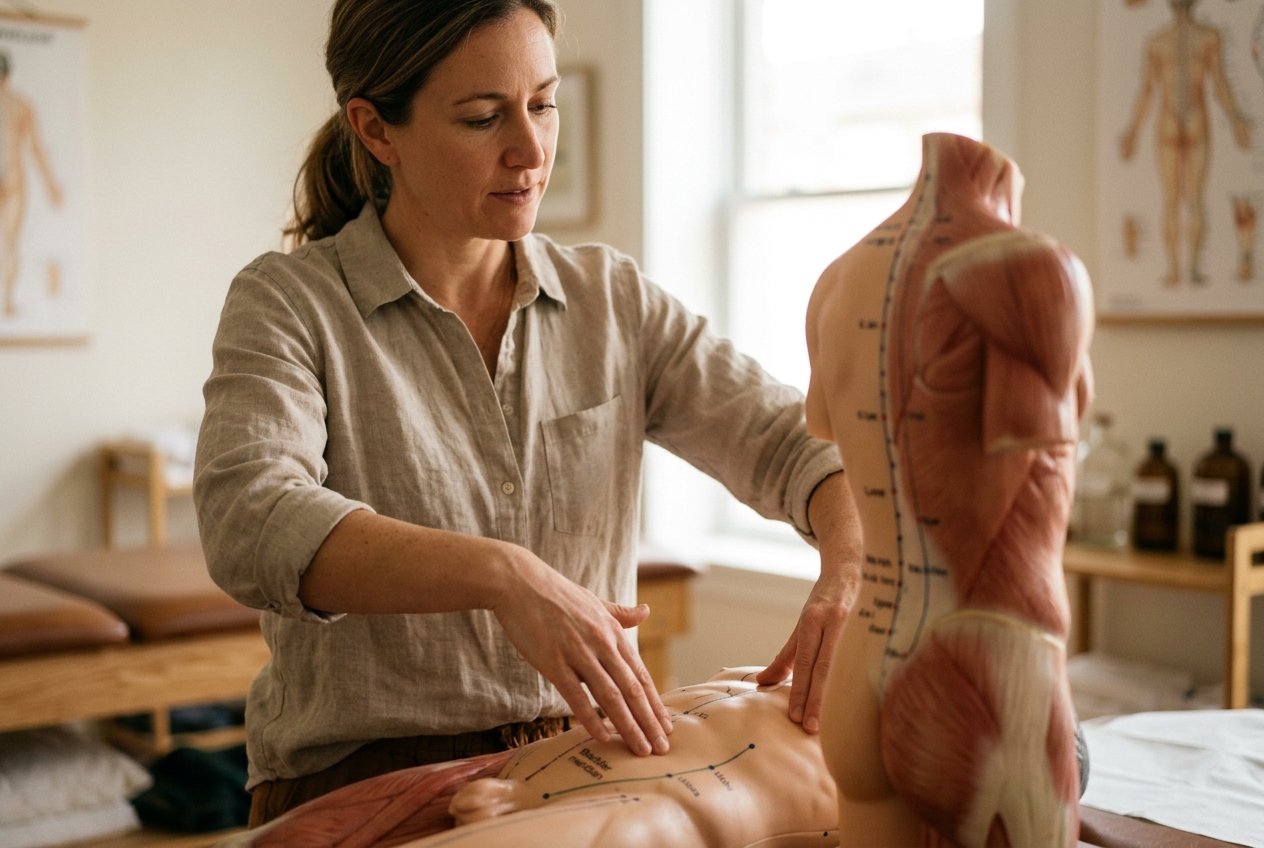
Traditional Chinese Medicine (TCM) mapped this interconnected visceral-somatic reality over two millennia ago through one of its most sophisticated clinical frameworks: the Mu-Shu Point Combination (俞募配穴法, Yu-Mu / Shu-Mu Pairing). By simultaneously engaging the ventral Front-Mu (募, "Gathering" or "Alarm") points located on the chest and abdomen with their corresponding dorsal Back-Shu (俞, "Transporting" or "Transmitting") points along the spine, classical physicians discovered they could regulate organ pathology from both sides of the body at once.
Where Western clinical medicine has historically treated somatic musculoskeletal pain and visceral autonomic dysfunction in distinct silos, modern neurobiology is arriving at the exact mechanism the ancients codified: somatovisceral reflex loops, shared dermatomal spinal segments, and autonomic tone modulation. Mastering this dual-axis architecture transforms basic bodywork into a clinical intervention capable of resolving acute functional distress while rebuilding constitutional vitality.
CLASSICAL THEORETICAL FOUNDATIONS
The Energetic Circuitry of Ling Shu and Nan Jing
To understand the profound clinical leverage of the Mu-Shu pairing strategy, one must examine its classical origin texts. The conceptual architecture was first systematically delineated in the foundational canons of Chinese medicine: the Huangdi Neijing (黄帝内经, The Yellow Emperor's Inner Classic), particularly within the Ling Shu (灵枢, Spiritual Pivot), and further refined in the profound dialectic of the Nan Jing (难经, The Classic of Difficulties).
In Chapter 67 of the Nan Jing, the text establishes the operational law governing visceral-energetic polarity:
"Yin diseases move to the Yang; Yang diseases move to the Yin. The Mu points gather Yin on the ventral surface, while the Shu points transport Yang along the dorsal spine."
This terse classical formula encapsulates a profound law of dynamic balance. In classical physiology, the twelve internal organs are bifurcated into the solid Zang organs (Yin—Heart, Lung, Spleen, Liver, Kidney, Pericardium), which store structural essence and vital substances, and the hollow Fu organs (Yang—Stomach, Large Intestine, Small Intestine, Bladder, Gallbladder, San Jiao), which transform, transport, and excrete matter.
When pathology strikes the body, the disease manifestation reflects this polar crossing: 1. Acute Fu Disorders (Yang in nature—spasm, inflammation, heat, fullness) rapidly project their distress forward onto the soft, vulnerable, Yin-dominated ventral torso. The Front-Mu points act as primary energetic hubs where the Qi of the respective viscus gathers, concentrates, and "alarms" the body through acute palpatory sensitivity. 2. Chronic Zang Disorders (Yin in nature—depletion, vacuity, structural degradation, exhaustion) project their deficiency backward onto the firm, structural, Yang-dominated dorsal column. The Back-Shu points serve as conduits where vital Qi and blood are transported directly into the deeper visceral matrix.
By coupling a Front-Mu point with its corresponding Back-Shu point, the practitioner creates a closed energetic loop. Applying pressure to the Front-Mu point unblocks stagnant, turbulent Qi in the anterior functional field, while stimulating the Back-Shu point infuses Yang energy and mobilizes constitutional nourishment from the posterior structural field. This dual vector ensures that neither acute symptom management nor long-term tonification is neglected.
MODERN NEUROANATOMY & SOMATOVISCERAL SYNERGY
Shared Metameres and Autonomic Calibration
Modern neurophysiology provides an elegant validation of this ancient bilateral methodology. The therapeutic efficacy of the Mu-Shu pairing does not rely merely on metaphor; it operates through the neuroanatomical wiring of the central and peripheral nervous systems.
1. Segmental Spinal Convergence (Somatovisceral Reflex Arcs)
Every internal organ receives sensory and motor innervation from specific spinal cord segments (metameres). Scientific research indexed on NCBI PubMed Central on Somatovisceral Reflex Mechanisms demonstrates that somatic sensory inputs from the body wall and visceral sensory inputs from internal organs converge upon identical interneurons in the dorsal horn of the spinal cord.
When an internal organ suffers from inflammation, ischemia, or mechanical distension, its visceral afferent fibers bombard the spinal cord segment with nociceptive signals. This creates a state of central sensitization known as "referred hyperalgesia."
The Front-Mu point of that organ is innervated by the anterior cutaneous branch of the ventral ramus of that exact same spinal nerve, while the Back-Shu point is innervated by the lateral/medial branches of the dorsal ramus of the identical spinal segment.
Stimulating both the ventral and dorsal cutaneous zones simultaneously saturates the shared dorsal horn segment with non-nociceptive somatic afferent signals (via thick, myelinated A-beta fibers, as well as modulated A-delta and C fibers). This dual somatic influx activates presynaptic inhibition, closing the spinal "gate" to visceral distress signals and interrupting pathological visceral spasms.
2. Autonomic Tone Recalibration: Sympathetic vs. Parasympathetic Balance
The Back-Shu points lie directly over the sympathetic paravertebral chain ganglia situated in the costovertebral gutters along the thoracic and lumbar spine. Mechanical or manual stimulation of these dorsal sites exerts a profound modulating effect on preganglionic sympathetic outflow, relieving vascular constriction in the visceral beds.
Conversely, Front-Mu stimulation—particularly along the midline of the Conception Vessel (Ren Mai) and adjacent Yin channels—modulates the visceral plexus and recruits parasympathetic tone mediated either by the Vagus nerve (Cranial Nerve X) for upper/middle abdominal viscera, or the pelvic splanchnic nerves (S2–S4) for lower pelvic organs.
As explored in peer-reviewed clinical research published in PubMed Central on Acupuncture and Autonomic Modulation, this dual somatic activation downregulates excessive sympathetic fight-or-flight outflow while elevating restorative parasympathetic vagal tone. The internal organ is released from neural strangulation, restoring peristalsis, glandular secretion, and microvascular perfusion.
THE MERIDIAN PATH: A JOURNEY THROUGH THE LIVING BODY
To locate and use these points without clinical instruments, you do not need complex anatomical tables; you need an intuitive, tactile understanding of your body’s physical geography.
The Anterior Yin Line: The Vessel of Conception (Ren Mai) and Chest Gateways
Imagine a vertical meridian river running directly up the anterior centerline of your torso, tracing the seam of a tailored shirt. This is the Conception Vessel (Ren Mai), the reservoir of all Yin energy in the human organism. It ascends from the firm upper ridge of the pubic bone, glides through the soft hollow of the navel, bisects the solar plexus, and scales the sternum to the base of the throat.
Branching outward from this central highway across the ribcage and abdomen are the front-facing gates of the individual meridians: * The Lung channel emerges high on the outer upper chest, nestled in the soft muscular hollow just below the collarbone where your shoulder joint meets the pectoral wall. * The Stomach and Spleen channels run in parallel lines down the abdominal plateau, midway between the central navel line and the outer muscular flanks.
This anterior landscape is soft, responsive, and immediately accessible. Because the abdominal wall lacks bony shielding, it reflects the state of your digestive, respiratory, and metabolic fire like a mirror.
The Posterior Yang Line: The Great Bladder Meridian River (Foot Taiyang)
Turn to the dorsal surface of the body, and you encounter the vast, protective shield of the Foot Taiyang Bladder meridian—the longest and most intricate channel in classical acupuncture, fully documented in the World Health Organization (WHO) Standard Acupuncture Point Locations.
Ascending over the crown of the head from the inner eyes, this energy highway plunges down the nape of the neck and splits into two parallel tracks on each side of the spinal column. The inner medial branch runs exactly 1.5 cun (approximately two finger-widths) lateral to the midline of the vertebral spinous processes.
As this channel cascades down the muscular valleys between the spine and the inner border of the shoulder blades, across the mid-back ribcage, and over the strong lumbar erector muscles, it forms a vertical switchboard: the Back-Shu points. Each pair of points sits adjacent to a specific vertebral level, aligning directly with the spinal nerve roots and autonomic ganglia that govern the corresponding organ deep within the thoracic and abdominal cavities.
THREE ESSENTIAL DUAL-AXIS PAIRINGS FOR CLINICAL PRACTICE
The table below outlines the primary classical Mu-Shu pairings, detailing their anatomical landmarks, shared spinal metameres, and primary clinical indications:
| Visceral System | Front-Mu Point (Yin Alarm) | Back-Shu Point (Yang Transport) | Spinal Metamere | Primary Clinical Indications |
|---|---|---|---|---|
| Middle Burner / Spleen-Stomach | CV12 (Zhongwan) — Midline epigastrium | BL20 (Pishu) — T11 paravertebral groove | T7–T12 (Thoracic Splanchnic) | Chronic bloating, post-prandial fatigue, brain fog, gastric reflux |
| Upper Burner / Lung System | LU1 (Zhongfu) — Subclavicular hollow | BL13 (Feishu) — T3 paravertebral groove | T1–T5 (Pulmonary Plexus) | Shallow breathing, chronic cough, immune exhaustion, grief |
| Lower Burner / Kidney Essence | CV4 (Guanyuan) — Lower abdominal midline | BL23 (Shenshu) — L2 paravertebral lumbar | L1–L3 / S2–S4 (Pelvic Splanchnic) | Lumbar instability, adrenal burnout, cold extremities, insomnia |
1. The Middle Burner Digestive & Metabolic Anchor
Ventral Front-Mu: CV12 (Zhongwan – "Central Venter")
Dorsal Back-Shu: BL20 (Pishu – "Spleen Transport")
- Physical Location (Front-Mu CV12): Place your index finger on your navel and your thumb on the bottom notch of your breastbone (the xiphoid process). CV12 lies precisely halfway along this line, in the soft center of your solar plexus.
- Physical Location (Back-Shu BL20): Reach around to your mid-back, just below the level of the eleventh rib (roughly level with the lowest sweep of your ribcage, two finger-widths lateral to the spine).
- Palpatory Diagnostic Assessment: In patients with functional dyspepsia, metabolic exhaustion, or food sensitivities, CV12 presents as sharply tender upon light-to-moderate fingertip pressure, often feeling tense like an inflated balloon. Conversely, BL20 presents dorsally as a doughy, hypotonic depression or a dense, fibrotic muscular knot within the spinal erectors.
- Target Sensations (De Qi Resonance): As documented in medical literature on the Neurobiological Basis of De Qi and Acupressure Resonance, stimulation produces a profound sensation consisting of a deep, spreading dull ache, accompanied by audible stomach rumbling (borborygmi), spontaneous salivation, and a release of diaphragmatic tension.
- Clinical Utilities: Resolves post-prandial distension, relieves mental overthinking ("spleen dampness"), mitigates acid reflux, and restores metabolic energy absorption.
2. The Upper Burner Respiratory & Immune Gateway
Ventral Front-Mu: LU1 (Zhongfu – "Central Treasury")
Dorsal Back-Shu: BL13 (Feishu – "Lung Transport")
- Physical Location (Front-Mu LU1): Slide your fingertips outward along the underside of your collarbone toward the shoulder. Right where the collarbone nears the shoulder joint, drop down about one thumb-width into the soft triangular hollow (the deltopectoral groove). LU1 sits in this tender notch.
- Physical Location (Back-Shu BL13): On your upper back, locate the upper inner corner of your shoulder blade. BL13 lies between the inner edge of the shoulder blade and the third thoracic vertebra (T3), two finger-widths from the spinal midline.
- Palpatory Diagnostic Assessment: Respiratory compromise, post-viral chest tightness, or unexpressed grief causes LU1 to feel acutely reactive, tight, and sore to the touch. BL13 demonstrates rigid muscular banding, trigger point tension, and cool skin temperature over the upper thoracic cage.
- Target Sensations (De Qi Resonance): A warm, radiating electrical tingling traveling down the inner arm toward the thumb, accompanied by an involuntary, effortless deep inhalation and a widening sensation across the clavicles.
- Clinical Utilities: Relieves chest tightness, alleviates acute and chronic bronchial irritation, stimulates mucosal immunity, and dissipates somatic patterns of postural closure and emotional sadness.
3. The Lower Burner Jing-Essence & Endocrine Foundation
Ventral Front-Mu: CV4 (Guanyuan – "Gate of Origin")
Dorsal Back-Shu: BL23 (Shenshu – "Kidney Transport")
- Physical Location (Front-Mu CV4): Lay four fingers horizontally across your lower belly directly below your navel. CV4 lies right along the midline, just below the lower edge of your pinky finger—in the pelvic bowl above the pubic bone.
- Physical Location (Back-Shu BL23): On your lower back, find the point directly level with your navel line. Move two finger-widths outward from the spinal column into the thick, ropy lumbar muscles (at the level of the second lumbar vertebra, L2).
- Palpatory Diagnostic Assessment: Chronic systemic exhaustion, hormonal imbalance, or lower back weakness causes CV4 to feel cold, flaccid, and structurally hollow upon palpation (as if your fingers could sink into an empty space). BL23 presents as either severe, tight guarding or deep, achy fatigue that craves sustained heat and pressure.
- Target Sensations (De Qi Resonance): A deep, nourishing wave of pelvic warmth, a softening of the lower lumbar hinge, a drop in resting heart rate, and an immediate sensation of grounded stability.
- Clinical Utilities: Restores constitutional reserves after severe burnout, alleviates nocturnal urination, stabilizes chronic low-back weakness, regulates the menstrual cycle, and supports autonomic restorative sleep.
COMPREHENSIVE EVENING PROTOCOL: THE RESTORATIVE METABOLIC RESET
A Step-by-Step Acupressure Clinical Routine for Post-Meal Bloating and Mental Exhaustion
This complete non-invasive protocol couples CV12 (Zhongwan) and BL20 (Pishu) to dissolve digestive stagnation, eliminate evening brain fog, and downregulate nervous hyperarousal before sleep.
Preparation & Posture
- Position: Lie comfortably on your back on a firm surface (such as a yoga mat or firm bed) with your knees bent at a 45-degree angle and your feet flat on the floor. This completely relaxes the rectus abdominis muscle, exposing the deep visceral pathways of the Front-Mu points.
- Breath Pacing: Adopt a relaxed diaphragmatic rhythm: inhale through your nose for 4 counts, hold gently for 2 counts, and exhale slowly through your mouth for 6 counts.
Step 1: Somatosensory Attunement (1 Minute)
Place both palms flat over your abdomen, resting your thumbs near your lower ribs and your fingertips over your navel. Close your eyes. Spend 60 seconds observing the temperature, movement, and tension of your abdominal wall without attempting to force change.
Step 2: Ventral Decompression at Front-Mu CV12 (Zhongwan) (2.5 Minutes)
- Hand Mechanics: Stack the middle three fingers of your dominant hand over the middle three fingers of your non-dominant hand. Place the combined fingertips on CV12 (halfway between the navel and breastbone base).
- Angle & Depth: Never press straight down into the abdominal aorta. Instead, angle your fingertips at a 45-degree angle upward toward your heart.
- Breath Synchronization: * As you inhale, maintain light surface contact. * As you exhale, allow your fingers to sink progressively deeper into the tissue, following the natural deflation of your abdomen. Sinking depth should reach 0.5 to 1.0 inch (1.5–2.5 cm), stopping immediately if you encounter a rigid muscular wall or sharp pulse.
- Mobilization: Once at depth, execute slow, microscopic clockwise circular mobilizations (about 1 revolution every 3 seconds). Maintain this steady, synchronized pressure for 2.5 minutes. You will feel a dull, pleasant ache and hear gastrointestinal gurgling.
Step 3: Dorsal Sympathetic Downregulation at Back-Shu BL20 (Pishu) (2.5 Minutes)
- Equipment/Positioning: Take two tennis balls or firm massage balls placed inside a sock.
- Placement: While remaining supine, slide the balls underneath your mid-to-lower back so that one ball sits on each side of your spine at the level of the eleventh thoracic vertebra (T11, two finger-widths away from the spinal bones, level with the bottom rib).
- Pressure Calibration: Allow your body weight to sink into the balls. Adjust your knee angle to regulate the pressure intensity to a comfortable 6 out of 10 on the subjective discomfort scale.
- Breath Synchronization: Inhale deeply, expanding your lower ribs directly against the resistance of the balls. Exhale slowly, feeling the paraspinal muscles surrender and melt around the pressure. Maintain this static, sustained release for 2.5 minutes.
Step 4: Dual-Axis Resonance & Integration (1 Minute)
Remove the balls from your back and return to lying flat. Place your warm right palm directly over CV12 (Zhongwan) on your front, and slide your left hand (palm facing the body) underneath your lower-middle back over the BL20 area. Breathe naturally for one minute, visualizing a warm, golden river of vital Qi flowing directly between your front and back hands, unifying the Yin and Yang axes of the digestive system.
SAFETY, SENSORY CALIBRATION, AND CLINICAL BOUNDARIES
While non-invasive acupressure carries an exceptional safety profile, rigorous clinical discipline requires strict adherence to somatic contraindications and sensory boundaries, as outlined by standard Traditional Chinese Medicine and Acupoint Meridian Networks safety guidelines.
Absolute and Relative Contraindications
- Pregnancy: Absolute caution must be exercised over the lower abdomen and lumbar region. Point CV4 (Guanyuan) and all lower abdominal Front-Mu points are strictly contraindicated during all stages of pregnancy due to their strong downward-bearing, pelvic-invigorating actions. Deep paraspinal pressure over the lumbosacral Back-Shu points (BL23 through BL34) must likewise be avoided.
- Vascular Vulnerability: Never apply deep, perpendicular pressure over the abdominal aorta (felt as a prominent, bounding pulsation beneath CV12). Always angle your pressure superiorly, and avoid sustained vascular compression.
- Acute Pathologies: Do not apply pressure over open wounds, acute inflammatory skin eruptions, unhealed surgical incisions, active hernia sites, or structural spinal fractures.
Decoding Somatic Sensation
Understanding the difference between therapeutic stimulation and tissue trauma is vital: * The "De Qi" Signal: Effective acupressure should evoke a sensation described in classical texts as Suan, Ma, Zhang, Zhong (酸、麻、胀、重)—soreness, numbness, distension, and heaviness. This is the physiological hallmark of somatosensory neural recruitment. It feels deep, satisfying, and therapeutic. * The Danger Signal: If you elicit sharp, burning, lancinating pain, or electric sensations shooting into the legs or arms, you are compressing a peripheral nerve or exceeding tissue tolerance. Ease off pressure immediately.
When to Seek Professional Intervention
Acupressure is a powerful self-care and regulatory modality, but it is not a substitute for medical evaluation. You must seek immediate evaluation from a licensed physician or acupuncturist if you experience: * Severe, unremitting abdominal pain with muscular rigidity (board-like abdomen). * Sudden, unexplained weight loss accompanied by chronic gastrointestinal bleeding. * Progressive motor weakness, loss of bowel/bladder control (cauda equina red flags). * Severe chest pain radiating to the jaw, neck, or left arm.
TODAY'S TAKEAWAY: THE TWO-MINUTE DESK RESET
You do not need an entire clinical suite or an hour of free time to harness the power of this dual-axis system. If you are sitting at your desk right now feeling drained, mentally foggy, or bloated from lunch, perform this instantaneous Two-Minute Zhongwan Reset:
- Step 1: Sit on the edge of your chair with your feet flat on the floor and your spine elongated. Uncross your legs.
- Step 2: Place your thumbs together, tips touching, directly over CV12 (Zhongwan), halfway between your navel and the base of your breastbone.
- Step 3: Inhale deeply. As you exhale, lean your torso forward about 15 degrees, allowing the weight of your upper body to press your thumbs gently inward and slightly upward into your upper stomach.
- Step 4: Hold this position for six slow, diaphragmatic breaths (approximately 120 seconds). With each exhalation, let your shoulders drop and feel the knot in your stomach soften.
- Step 5: Slowly sit upright, release your hands to your lap, and take one full breath. Notice the immediate rush of warmth into your midsection, the spontaneous drop in shoulder tension, and the crisp return of mental focus.
By engaging the Mu-Shu system, you have bridged the ancient wisdom of classical medicine with modern neurobiology—taking command of your own autonomic health from the inside out.