Crossing Points: Navigating Multi-Meridian Intersections, Synergistic Network Hubs, and Convergence Acupressure Protocols
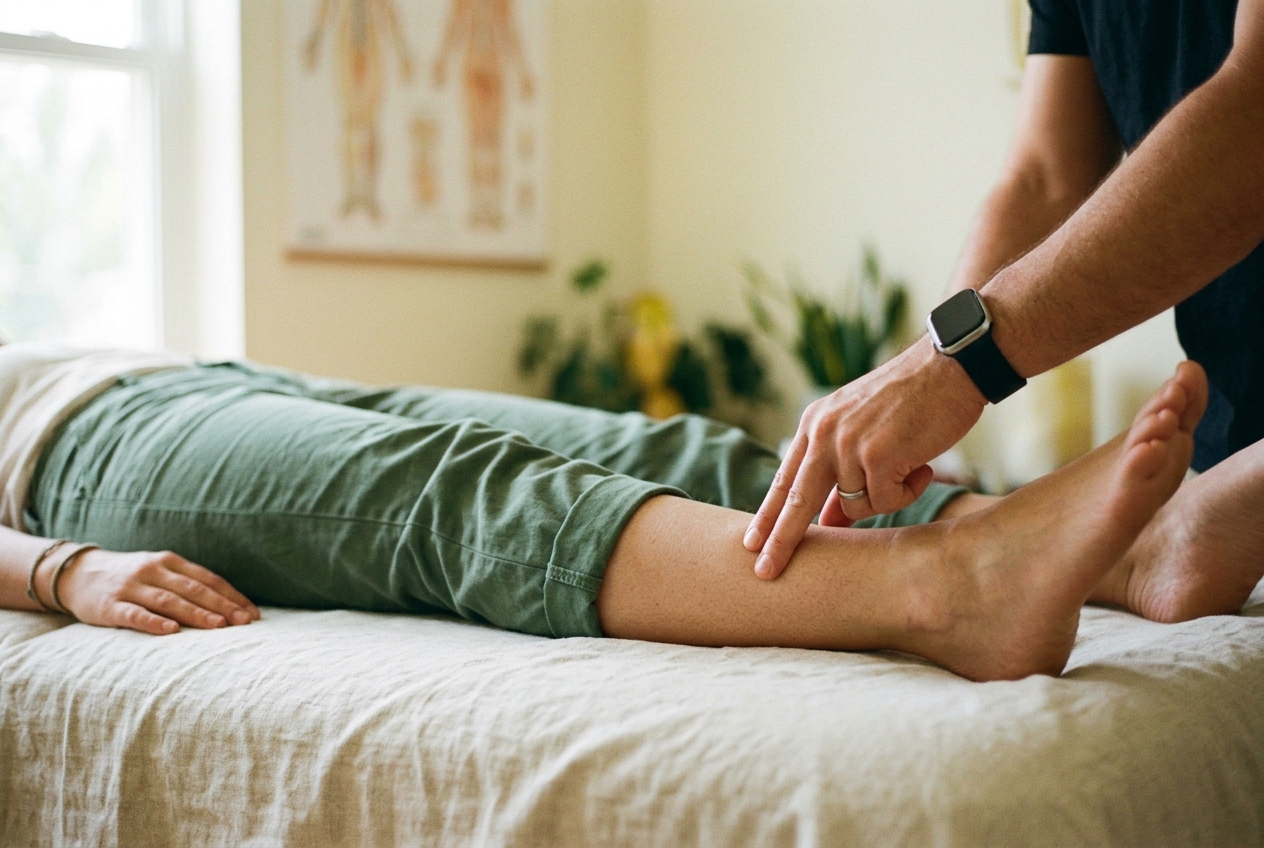
Consider a constellation of symptoms familiar to modern clinical practice: a patient presents with persistent mid-afternoon cognitive fatigue, accompanied by low-grade epigastric distension, shallow thoracic breathing, and an insidious tightness wrapping around the suboccipital margin and inner calves. In conventional siloed examinations, these manifestations are frequently fragmented into distinct diagnoses—tension-type headache, functional dyspepsia, and chronic sympathetic overactivity. The patient is offered separate interventions for the gut, the musculature, and the nervous system, yet the underlying dysregulation remains unresolved.
+-------------------------------------------------------------------------------+
|                       THE DYSREGULATION TRIAD IN MODERN LIFE                   |
|                                                                               |
|    [ Cranial Rigidity ] <----------> [ Enteric Stasis ] <----------> [ Neuroendocrine Fatigue ]
|     Suboccipital tension,             Epigastric bloating,            Adrenal-HPA strain,
|     headaches, mental haze            slow gastric emptying           cold feet, lower-leg ache
|                                                                               |
|               NEXUS SOLUTION: Multi-Channel Crossing Points (Jiao-Hui Xue)     |
+-------------------------------------------------------------------------------+
Traditional Chinese Medicine (TCM) approaches this presentation not as a set of disconnected pathologies, but as a systemic traffic jam occurring at primary anatomical and energetic intersections. When physiological stress accumulates, it concentrates at multi-channel nexus points known as Crossing Points (Jiao-Hui Xue, 交会穴).
First systematically codified by the physician Huangfu Mi in his seminal 3rd-century treatise Zhen Jiu Jia Yi Jing (The Systematic Classic of Acupuncture and Moxibustion), Jiao-Hui Xue are specialized acupoints where two or more primary meridians (Jingmai) or Extraordinary Vessels (Qi Jing Ba Mai) physically and functionally intersect.
Classical channel theory identifies hundreds of distinct loci across the body, but crossing points occupy an elevated taxonomic hierarchy. While standard points regulate the homeostatic flow of a single meridian pathway, a crossing point acts as a biological multiplexer—a high-density biological switchboard capable of redistributing Qi, modulating microvascular perfusion, and re-patterning peripheral sensory input across multiple somatic and visceral systems simultaneously. By understanding the topological and neuro-fascial mechanics of these intersections, we obtain an actionable clinical framework for addressing multi-system disorders through targeted, non-invasive manual interventions.
2. The Meridian Path — A Journey Through the Body
To understand how crossing points operate, one must look past historical esotericism and observe the physical substrate through which meridians travel: the living fascial matrix and its embedded neurovascular bundles. Classical TCM texts describe meridians as pathways that traverse intermuscular valleys, run along the contours of long bones, and plunge deeply into internal visceral cavities.
Modern anatomical research, pioneered by cell biologist Dr. Helene Langevin and colleagues investigating mechanotransduction in connective tissue, demonstrates that traditional meridian trajectories show an eighty percent correspondence with intermuscular connective tissue planes and interfascial cleavages.
When manual pressure is applied to the skin, mechanical force is transmitted through the extracellular matrix (ECM). Interstitial fibroblasts undergo cytoskeletal remodeling, releasing purines such as adenosine triphosphate (ATP), which rapidly degrades into adenosine—a potent endogenous anti-inflammatory and antinociceptive agent. At the same time, this mechanical signal travels along continuous fascial sheets that link distant muscular compartments to internal organ investitures.
At the level of the central nervous system, crossing points represent zones of high-density neural convergence. When multiple meridians intersect anatomically, primary somatic afferent fibers from different peripheral dermatomes and myotomes project onto overlapping spinal segments.
According to the classical Gate Control Theory of pain modulation and modern studies on the mechanisms of somatic afferent convergence in the spinal dorsal horn, sustained mechanoreceptive stimulation of large-diameter myelinated $A\beta$ fibers at these intersecting hubs fires inhibitory interneurons in the substantia gelatinosa. This inhibits the transmission of chronic nociceptive signals carried by unmyelinated $C$ fibers across multiple visceral and somatic fields.
Consider the physical journey along these intersecting highways:
- The Medial Leg Highway: Trace the smooth inner border of your shinbone upward from the ankle. Here, deep fascial sheets separate the calf musculature (soleus and gastrocnemius) from the deeper flexors (flexor digitorum longus and tibialis posterior). Within this intermuscular groove run the pathways of the Spleen, Liver, and Kidney meridians, alongside the posterior tibial neurovascular bundle.
- The Abdominal Axial Line: Follow the midline of the belly from the pubic crest up to the base of the ribcage. This is the linea alba, an unvascularized fibrous band where the aponeuroses of the external oblique, internal oblique, and transversus abdominis interlace. This structural midline hosts the Conception Vessel (Ren Mai), serving as the anchoring junction for autonomic branches communicating with the digestive organs.
- The Cervicothoracic Hinge: Palpate the base of the neck where the mobile cervical spine transitions into the rigid thoracic cage. The prominent vertebral prominence marks a profound musculoskeletal bridge where the superficial and deep investing layers of cervical fascia merge with the dorsal back musculature, concentrating the six Yang channels of the body.
- The Suboccipital Basin: Place your fingers at the base of the skull, in the hollows just lateral to the thick spinal rope muscles. Here, beneath the upper trapezius and sternocleidomastoid tendons, lies the suboccipital triangle—a critical neurovascular portal rich in muscle spindles and proprioceptive receptors, where cranial Yang channels cross into the neurocranium.
3. Key Crossing Points You Can Press Right Now
The World Health Organization (WHO) Standard Acupuncture Point Locations provides a globally standardized anatomical taxonomy for identifying these classical loci. Below are detailed physical, physiological, and clinical profiles for the most potent multi-channel crossing points in the human body.
========================================================================================
                                 PRIMARY CROSSING POINTS MATRIX
========================================================================================
Point Code  Classical Name   Channels Intersecting                  Primary Neuro-Visceral Target
----------------------------------------------------------------------------------------
SP6         Sanyinjiao       Spleen, Liver, Kidney                  Enteric, Endocrine, Pelvic Autonomics
GV14        Dazhui           Governing Vessel + 6 Yang Channels     Thermoregulation, Sympathetic Tone
CV12        Zhongwan         Conception Vessel, Stomach, SI, SJ     Gastric Pacemaker, Enteric Nervous System
GB20        Fengchi          Gallbladder, Sanjiao, Yang Qiao/Wei    Cranial Hemodynamics, Trigeminal Axis
CV4 / CV3   Guanyuan/Zhongji Conception Vessel + 3 Foot Yin         Urogenital, Deep Pelvic Parasympathetics
========================================================================================
A. SP6 (Sanyinjiao, 三阴交) — The Three Yin Intersection
Anatomical Location & Palpation
Sanyinjiao is located on the medial aspect of the lower leg. To locate it without a measuring tape, place the outer edge of your four fingers (held flat together) across the inner leg, starting directly from the highest prominence of your inner ankle bone (medial malleolus). SP6 lies immediately adjacent to the back border of your shinbone (posterior border of the medial tibia), roughly four finger-widths above the ankle.
When your thumb rolls over the bone's edge into the soft tissue, you will sink into a distinct fascial depression between the tibia and the calf muscles. Upon palpation, the tissue here frequently reveals a taut, fibrous band with heightened mechanical sensitivity compared to adjacent zones.
Neuro-Endocrine & Enteric Mechanisms
SP6 is the premier lower-body multiplexer, representing the structural convergence of: 1. The Foot Taiyin (Spleen — metabolic transformation, fluid distribution, muscular nourishment). 2. The Foot Jueyin (Liver — myofascial tension regulation, smooth hepatic outflow, emotional reactivity). 3. The Foot Shaoyin (Kidney — constitutional vigor, adrenal regulation, fluid/electrolyte equilibrium).
Anatomically, SP6 overlies the posterior tibial nerve, which originates from the L4 through S2 spinal roots. Tactile stimulation here transmits mechanosensory afference into the lumbosacral spinal cord, directly influencing the pelvic splanchnic nerves and modulating parasympathetic innervation to the pelvic viscera, descending colon, and reproductive organs.
Furthermore, clinical trials listed in the National Center for Biotechnology Information (NCBI) database demonstrate that mechanical stimulation of SP6 modulates the hypothalamic-pituitary-ovarian (HPO) and hypothalamic-pituitary-adrenal (HPA) axes, normalizing autonomic microcirculation and reducing visceral smooth muscle spasms.
Palpatory Sensation (Deqi)
When accurate contact is established, the practitioner or patient will experience Deqi (得气)—a dull, spreading ache, localized distension, or a gentle upward or downward radiating warmth along the inner leg, distinct from sharp, superficial pain.
Pressing Protocol
- Direction: Angle the force at a $90^\circ$ perpendicular vector to the skin, pressing slightly anteriorly against the posterior edge of the tibia rather than simply compressing the calf muscle mass.
- Firmness: Moderate to deep sustained pressure (calibrated to generate clear Deqi without triggering defensive muscle guarding).
- Duration: $2\text{ to }3\text{ minutes}$ per limb, synchronized with deep diaphragmatic respirations.
- Targeted Indications: Menstrual cramping, premenstrual mood volatility, lower abdominal distension, insomnia due to mental overwork, and chronic lower-limb circulatory heaviness.
B. GV14 (Dazhui, 大椎) — The Great Vertebra
Anatomical Location & Palpation
Dazhui is located on the posterior midline of the body, at the base of the neck. To locate this junction, flex your head forward so your chin approaches your chest. Run your fingers down the back of your neck along the midline until you encounter the most prominent bony projection: the spinous process of the 7th cervical vertebra (C7, vertebra prominens).
To verify you have isolated C7 and not the first thoracic vertebra (T1), keep your finger on the bone and rotate your head slowly from side to side; the C7 vertebra will rotate noticeably under your finger, whereas the underlying T1 vertebra remains relatively stationary. GV14 resides directly in the soft depression immediately beneath the spinous process of C7.
Neuro-Immunological & Thermoregulatory Mechanisms
GV14 represents the confluence of the Governing Vessel (Du Mai, the "Sea of Yang Channels") and all six Yang meridians of the hands and feet (Large Intestine, Small Intestine, Sanjiao, Stomach, Bladder, and Gallbladder). It is the most concentrated thermal and autonomic regulator in the somatic meridian system.
Neuro-anatomically, GV14 corresponds to the C8–T1 posterior spinal rami and is located adjacent to the sympathetic trunk ganglia. Stimulating this locus exerts a profound influence on systemic thermoregulation, peripheral cutaneous vasodilation, and central immune activation.
Acupressure here activates descending inhibitory pathways from the brainstem reticular formation, down-regulating sympathetic hyperactivity (such as systemic hot flashes, cold sweats, and acute stress-induced tachycardia) while enhancing cervical microvascular perfusion.
Palpatory Sensation
A spreading, comforting sensation of localized warmth that expands across the upper trapezius and shoulder girdle, often accompanied by an immediate reflexive reduction in baseline respiratory rate.
Pressing Protocol
- Direction: Direct perpendicular pressure into the interspinous space, oriented slightly superiorly toward the crown of the head.
- Firmness: Firm, broad contact using the pad of the middle finger or thumb.
- Duration: $1.5\text{ to }3\text{ minutes}$, incorporating slow neck rotations or gentle isometric neck extensions.
- Targeted Indications: Systemic fatigue, feelings of an oncoming environmental chill, upper back stiffness from sedentary posturing, mental fog, and tension across the upper shoulder girdle.
C. CV12 (Zhongwan, 中脘) — The Middle Epigastrium
Anatomical Location & Palpation
Zhongwan sits on the anterior midline of the abdomen. To locate it with precision, place one hand at the base of your breastbone (the inferior tip of the xiphoid process at the center of the ribcage angle) and your other hand at the center of your navel (umbilicus).
Measure the line connecting these two landmarks; CV12 lies exactly halfway along this path, resting upon the dense fibrous tissue of the linea alba. When palpating with a relaxed abdominal wall, you will feel a mild, yielding hollow within the tendon sheath.
Enteric & Autonomic Mechanisms
CV12 is both the Front-Mu (Alarm) point of the Stomach and the central crossing hub connecting: 1. The Conception Vessel (Ren Mai). 2. The Stomach Meridian (Foot Yangming). 3. The Small Intestine Meridian (Hand Taiyang). 4. The Triple Burner (Hand Shaoyang).
From an embryological and neurological standpoint, CV12 overlies the celiac plexus (the "abdominal brain") and is innervated by the anterior cutaneous branches of the 7th and 8th intercostal nerves ($T7\text{--}T8$). Mechanical manipulation of this point modulates the enteric nervous system (ENS), which operates via intrinsic pacemaker networks—the interstitial cells of Cajal.
Sustained, gentle compression of CV12 sends viscerosomatic inputs that down-regulate splanchnic sympathetic tone while elevating vagal (parasympathetic) efferent activity to the stomach and duodenum. This normalizes gastric acid secretion, coordinates gastric emptying, and relieves functional epigastric spasm.
Palpatory Sensation
A deep, soft visceral easing sensation, frequently followed within sixty to ninety seconds by audible borborygmi (stomach gurgling) and an involuntary spontaneous relaxation sigh.
Pressing Protocol
- Direction: Perpendicular into the midline, pressing slowly on the patient's exhalation to access the sub-fascial planes without causing defensive abdominal muscle guarding.
- Firmness: Light to medium; never use sharp or aggressive force in the epigastrium.
- Duration: $2\text{ to }3\text{ minutes}$ using rhythmic circular friction or continuous gentle compression synchronized with diaphragmatic breath cycles.
- Targeted Indications: Postprandial fullness, acid reflux, epigastric distension caused by psychological stress ("nervous stomach"), and disrupted appetite.
D. GB20 (Fengchi, 风池) — The Wind Pool
Anatomical Location & Palpation
Fengchi is located bilaterally at the posterior base of the cranium. To find it, clasp your hands behind your head with your thumbs pointing downwards. Allow your thumbs to slide upward into the large depressions directly beneath the occipital bone, situated between the lateral border of the upper trapezius muscle and the medial border of the sternocleidomastoid muscle.
The points feel like two distinct thumb-sized pools or wells nestled directly under the cranial shelf.
Cranial Hemodynamics & Sensory De-Sensitization
GB20 represents the complex cranial intersection of: 1. The Gallbladder Meridian (Foot Shaoyang). 2. The Sanjiao Meridian (Hand Shaoyang). 3. The Yang Motility Vessel (Yang Qiao Mai). 4. The Yang Linking Vessel (Yang Wei Mai).
Anatomically, GB20 sits directly over the suboccipital triangle, through which pass the greater occipital nerve and the vertebral artery. The suboccipital muscles contain one of the highest densities of muscle spindles per gram of tissue anywhere in the human body, acting as sensitive barometers for emotional stress, visual strain, and postural forward-head drift.
Acupressure at GB20 relieves physical entrapment of the greater occipital nerve, mitigates central sensitisation within the trigeminocervical nucleus (the neural engine driving tension-type and migraine headaches), and improves posterior cerebral and basilar microvascular blood flow.
Palpatory Sensation
A profound, penetrating ache that often radiates anteriorly toward the temples, forehead, or retro-orbital space, signaling therapeutic engagement with the trigeminal pain pathways.
Pressing Protocol
- Direction: Press firmly upward and inward toward the bridge of the nose or opposite eyeball, anchoring the thumb pads under the base of the skull.
- Firmness: Medium to deep sustained pressure.
- Duration: $2\text{ to }3\text{ minutes}$ while maintaining slow, nasal breathing.
- Targeted Indications: Tension headaches, ocular fatigue from screen glare, neck stiffness, dizziness, and mental agitation.
E. Lower Pelvic Yin Convergence: CV4 (Guanyuan) and CV3 (Zhongji)
While SP6 manages the lower extremities, the lower abdominal midline houses CV4 (Guanyuan, 关元) and CV3 (Zhongji, 中极). Located three and four thumb-widths below the navel respectively, these points represent the trunk-level intersections where the three Foot Yin channels (Spleen, Liver, Kidney) physically weave into the Conception Vessel (Ren Mai).
These hubs overlie the hypogastric plexus and serve as master switches for pelvic floor tonicity, bladder autonomic control, and reproductive vitality. Gentle, warming palpatory pressure here calms visceral distress and provides a physical anchor for autonomic grounding.
4. A Point Combination for One Common Issue
The Modern Dilemma: Screen-Induced Sympathetic Lockout & Digestive Shutdown
Consider the common modern clinical presentation: an individual finishes an intense ten-hour workday seated at a computer. The nervous system is trapped in sympathetic dominance, the suboccipital region is rigid from sustained visual focus, the midsection feels compressed and bloated from sitting, and the lower legs feel heavy and stagnant.
Rather than treating these as separate problems, we can apply a Three-Node Triaxial Decompression Protocol that simultaneously resets the cranial, enteric, and peripheral circulation using our primary crossing points.
The Step-by-Step Evening Protocol
1. Environmental & Postural Preparation ($1\text{ minute}$)
Lie supine on a firm, comfortable surface (such as a yoga mat or bed). Bend your knees at a $90^\circ$ angle with your feet resting flat on the floor, hip-width apart. This immediately slackens the psoas and abdominal wall musculature, allowing clear access to the deep fascial planes without muscular resistance.
2. Step One: Cranial De-escalation via GB20 ($3\text{ minutes}$)
- Action: Interlace your fingers behind your neck, sliding your thumbs into the bilateral hollows of GB20 beneath the base of your skull.
- Pressure Vector: Hook your thumbs upward and slightly inward toward the center of your forehead. Allow the weight of your head to rest back onto your thumbs.
- Breathing: Inhale through your nose for a count of four; exhale slowly through your lips for a count of six. With each exhalation, allow the suboccipital muscles to melt around your thumb pads.
- Somatic Goal: Soften the hypertonic suboccipital cradle, relieving retro-orbital tension and down-regulating trigeminal sensory overdrive.
3. Step Two: Enteric Unwinding via CV12 ($3\text{ minutes}$)
- Action: Place the overlapping pads of your index, middle, and ring fingers of both hands directly onto the midpoint between your breastbone and navel (CV12).
- Pressure Vector: As you inhale, maintain soft contact. As you exhale, allow your fingers to sink $1\text{ to }1.5\text{ inches}$ perpendicularly into the linea alba. Do not poke; apply a broad, warm compression.
- Technique: Perform slow, micro-circular kneading movements (the diameter of a coin) clockwise.
- Somatic Goal: Disarm celiac plexus tension, release diaphragm spasm, and reactivate parasympathetic gastrointestinal peristalsis.
4. Step Three: Fluid & Neuroendocrine Settling via SP6 ($4\text{ minutes}$)
- Action: Drop your knees outward into a relaxed butterfly stretch, or cross your left ankle over your right knee. Locate SP6 four finger-widths above the medial malleolus, behind the tibial edge.
- Pressure Vector: Apply sustained thumb pressure directed perpendicularly against the back border of the bone. Hold continuously for $2\text{ minutes}$, feeling for a dull, warm, spreading ache. Switch limbs and repeat on the right leg.
- Somatic Goal: Clear metabolic waste from the lower extremities, harmonize the three lower Yin channels, and settle pelvic blood flow for restorative sleep.
5. Safety & Sense
While acupressure is an extraordinarily safe, non-invasive modality, working with high-potency crossing points requires clear anatomical discernment, respect for physiological boundaries, and strict adherence to clinical contraindications.
+-------------------------------------------------------------------------------+
|                             SAFETY & CAUTION MATRIX                           |
+-------------------------------------------------------------------------------+
|  PREGNANCY WARNING:                                                           |
|  • SP6 (Sanyinjiao) is STRICTLY CONTRAINDICATED throughout pregnancy.          |
|    Stimulation can induce uterine contractions and initiate labor.            |
|  • CV3 and CV4 are likewise contraindicated in pregnancy.                      |
+-------------------------------------------------------------------------------+
|  PRESSURE THRESHOLDS:                                                         |
|  • Therapeutic "Deqi": Dull ache, distension, warmth, localized soreness.     |
|  • Pathological Pain: Sharp, electric, burning, or sharp pinching.           |
|    (If sharp pain occurs, ease pressure immediately and verify landmarks).   |
+-------------------------------------------------------------------------------+
|  CLINICAL REFERRAL TRIGGERS:                                                  |
|  • Sudden-onset "thunderclap" headaches (Rule out vascular catastrophe).      |
|  • Acute unyielding abdominal pain with guarding/rebound tenderness.          |
|  • Unilateral leg swelling with heat and redness (Rule out DVT).              |
+-------------------------------------------------------------------------------+
Critical Contraindications
- Pregnancy Precautions: SP6 (Sanyinjiao) is strictly contraindicated during pregnancy (from conception until the 38th week of gestation). Classical literature and modern obstetric acupuncture data confirm that strong stimulation of SP6 activates oxytocic reflex pathways, increases myometrial contractility, and can trigger uterine contractions or induce premature labor. Deep acupressure on lower abdominal crossing points (CV3 and CV4) is also strictly forbidden during pregnancy.
- Local Tissue Compromise: Never apply direct or deep manual pressure over areas of broken skin, acute dermatitis, open wounds, active infections, burn sites, varicose veins, or localized vascular inflammation (thrombophlebitis).
- Pressure Calibration: The goal of acupressure is never to inflict sharp, bruising trauma. Therapeutic stimulation operates within the sensation of Deqi—a comfortable, deep, dull ache often described as "pleasurable soreness." If you feel a sharp, electric, or burning sensation, you may be impinging directly upon a superficial nerve sheath or blood vessel; immediately reduce pressure and re-palpate the anatomical landmarks.
When to Seek Clinical Intervention
Self-administered acupressure is a powerful daily self-care practice, but it cannot replace formal medical evaluation. If you experience sudden, severe headaches unlike any previous experience ("thunderclap" onset), unexplained acute abdominal pain accompanied by fever or vomiting, unexplained calf swelling with localized heat, or chronic unyielding symptoms, consult a licensed physician and a board-certified, licensed acupuncturist for comprehensive diagnostic workups.
6. Today's Takeaway
+-------------------------------------------------------------------------------+
|                           YOUR 2-MINUTE SOMATIC RESET                         |
|                                                                               |
|   Target Point: GB20 (Fengchi / Wind Pool)                                    |
|   Target Need:  Immediate relief from screen fatigue, neck tension, brain fog |
|                                                                               |
|   1. Clasp hands behind head; rest thumbs in the two hollows under the skull. |
|   2. Inhale deeply; tilt your head slightly back into your thumbs.            |
|   3. Exhale for 6 seconds while pressing UP and IN toward your eyes.          |
|   4. Maintain steady, gentle pressure for 10 deep, conscious breaths.         |
+-------------------------------------------------------------------------------+
You do not need an hour of free time or specialized tools to access the regulatory power of the human fascial and nervous systems. Right now, before moving on to your next task:
- Drop your shoulders away from your ears.
- Reach both hands behind your head and let your thumb pads settle into the warm hollows of GB20 (Fengchi) directly beneath the base of your skull.
- Close your eyes, breathe in slowly through your nose, and as you exhale, apply a steady, upward-and-inward pressure into that cranial shelf.
- Maintain this contact for ten deep, deliberate breaths.
In less than one hundred and twenty seconds, you are engaging a crossing point that has served as a master biological switchboard for over two millennia. By bridging classical meridian topology with contemporary neuro-fascial science, you take direct, conscious stewardship of your internal physiological state.