Four Command Points (Si Zong Xue) Meridian Dynamics: Governing Regional Anatomical Zones, Distal Neurovascular Regulation, and Somatosensory Homeostasis in Traditional Chinese Medicine
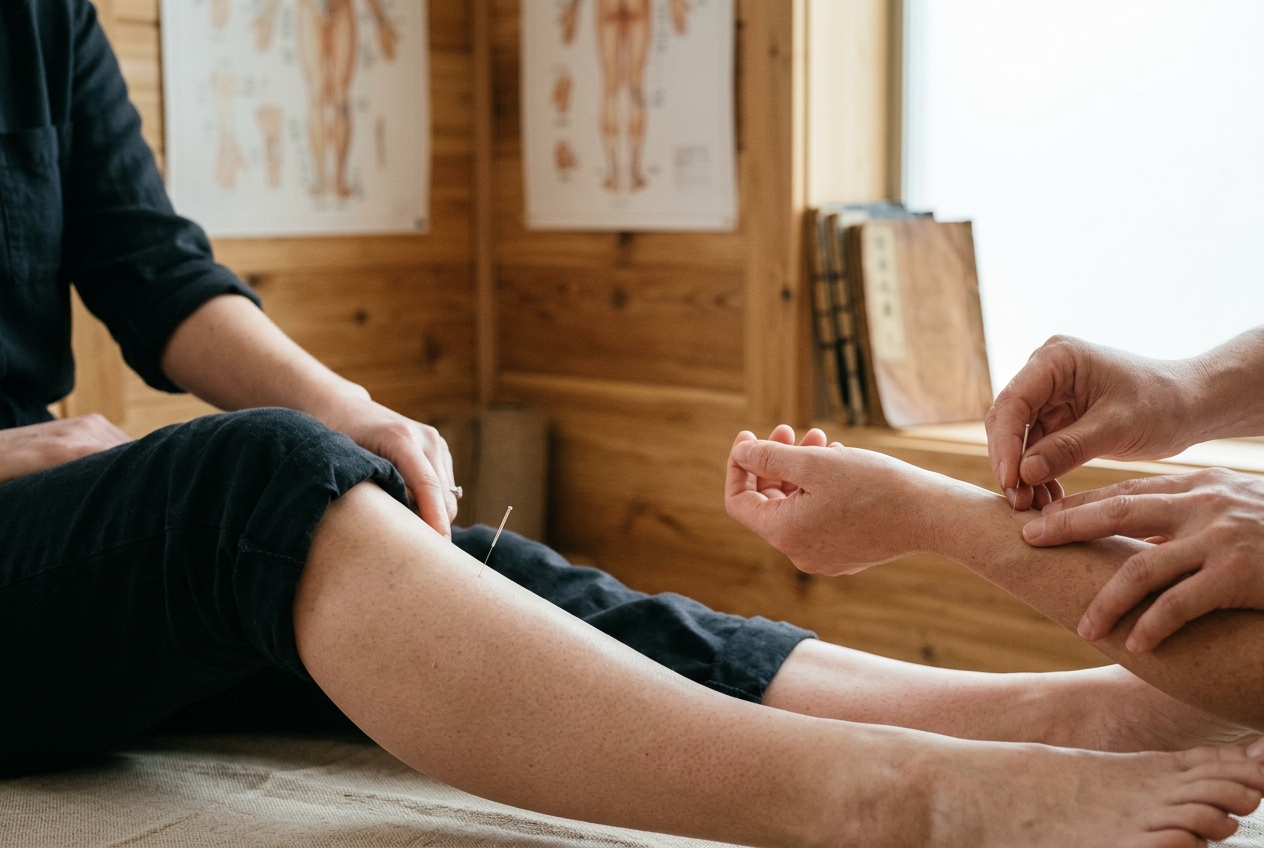
You bend down to tie a shoelace or lift a modest grocery bag from the car boot, and in an instantaneous fraction of a second, your lower back seizes. The paraspinal musculature locks into an iron spasm; every millimeter of movement radiates a sharp, incapacitating ache across the lumbosacral junction. Intuitively, your hands fly directly to your lower back, pressing hard against the lumbar vertebrae in a desperate bid for relief. Yet, when an experienced acupuncturist or somatic clinician evaluates this presentation, their hands rarely linger on the lumbar spine. Instead, their fingers slide down to the crease behind your knee, palpating the popliteal fossa to find a tender, pulsating indentation known as Weizhong (BL40). With firm, rhythmic pressure or the insertion of a single filiform needle at this distal site, the locked lumbar erectors suddenly release, allowing breath and flexion to return to the torso.
This clinical phenomenon illustrates one of the most profound paradoxes in classical medicine: the capacity of distal extremity points to command distant, major anatomical territories. Whether it is the sudden relief of a blinding occipital headache through a point on the lateral wrist, the cessation of a throbbing toothache via the muscular web between the thumb and index finger, or the soothing of violent gastric reflux by stimulating a point beneath the knee, distal acupuncture points consistently exert therapeutic mastery over the core, trunk, and sensory orifices.
In Traditional Chinese Medicine (TCM), this systematic remote governance is formalized in the doctrine of the Four Command Points (Si Zong Xue - 四总穴). Far from mystical superstition, this classical framework represents an early, sophisticated mapping of somatotopic neuroanatomy, myofascial force transmission, and dermatomal-visceral cross-talk.
+-----------------------------------------------------------------------------------------+
|                                THE SIX COMMAND AXES                                     |
+----------------------+--------------------+---------------------------------------------+
| Command Point        | Governed Territory | Primary Neurological & Myofascial Mechanism |
+----------------------+--------------------+---------------------------------------------+
| Zusanli (ST36)       | Abdomen & GI Tract | Deep Peroneal / Vagal-Parasympathetic Loop  |
| Weizhong (BL40)      | Lumbar Spine & Back| Tibial Nerve / Superficial Back Line Fascia |
| Lieque (LU7)         | Head & Posterior Neck| Radial Nerve / Trigeminocervical Complex   |
| Hegu (LI4)           | Face & Oral Cavity | First Dorsal Interosseous / Cortical S1 Map |
| Neiguan (PC6) [Ext]  | Chest & Epigastrium| Median Nerve / Vagal-Cardiac Homeostasis    |
| Shuigou (DU26) [Ext] | Face, Brain & Spirit| Trigeminal CN V2 / Sympathetic Resuscitation|
+----------------------+--------------------+---------------------------------------------+
2. What This System Does: The Architecture of Distal Governance
The foundational codification of the Four Command Points first appeared in the Ming Dynasty text Zhen Jiu Da Cheng (The Great Compendium of Acupuncture and Moxibustion, 1601), synthesizing the mnemonic verses of the Si Zong Ge (Song of the Four Commands):
“Du fu san li liu, yao bei wei zhong qiu, tou xiang xun lie que, mian kou he gu shou.”
(For disorders of the abdomen and stomach, seek Zusanli [ST36]; for the lumbar region and back, seek Weizhong [BL40]; for the head and posterior neck, look to Lieque [LU7]; for the face and mouth, gather at Hegu [LI4].)
During the late Ming and Qing dynasties, clinical observation expanded this tetrad into the Six Command Points (Liu Zong Xue), adding Neiguan (PC6) to govern the chest, heart, and epigastrium, and Renzhong/Shuigou (DU26) for acute cranial emergencies, loss of consciousness, and sensory organ restoration.
                              [ DU26 Shuigou ]
                        (Cranial Clearance / Resuscitation)
                                      |
       [ LI4 Hegu ] <-----------------+-----------------> [ LU7 Lieque ]
 (Face, Jaw, Oral Cavity)             |             (Occiput, Cervical Spine)
                                      |
                               [ PC6 Neiguan ]
                           (Chest, Heart, Epigastrium)
                                      |
                               [ ST36 Zusanli ]
                         (Abdomen, Stomach, GI Tract)
                                      |
                               [ BL40 Weizhong ]
                          (Lumbar Spine, Sacrum, Back)
To modern biomedical science, the notion that puncturing an extremity can treat visceral organs or remote cranial structures was long viewed with skepticism. However, contemporary neuroimaging, electrophysiology, and myofascial dissection have unveiled the precise mechanisms through which these distal hubs operate.
Somatotopic Disproportion and Cortical Magnification
The human primary somatosensory cortex ($S_1$) and motor cortex ($M_1$) do not represent the body in proportional physical dimensions. As mapped in the classic Penfield cortical homunculus, distal structures—specifically the hands, feet, and face—possess a massively disproportionate density of mechanoreceptors, proprioceptors, and nociceptive afferents, occupying extensive territory within the postcentral gyrus. Stimulation of high-density distal sites like Hegu (LI4, situated in the first dorsal interosseous muscle) or Zusanli (ST36, over the tibialis anterior muscle) elicits extensive neuromodulatory cascades across the central nervous system, driving neuroplastic gating mechanisms that proximal or local trunk points cannot replicate. Functional neuroimaging studies indexed via NCBI PubMed: Functional MRI Mapping of LI4 and ST36 demonstrate that stimulation of LI4 and ST36 selectively modulates limbic-paralimbic-neocortical networks (including the anterior cingulate cortex, insula, and amygdala), far exceeding the regional neural activation seen with local tissue stimulation.
Spinal Gate Control and Ascending-Descending Pain Modulation
Distal stimulation relies heavily on the Gate Control Theory of Pain, formulated by Ronald Melzack and Patrick Wall. Mechanoreceptive $A\beta$ and proprioceptive afferent fibers stimulated at distal acupoints project to the dorsal horn of the spinal cord, exciting inhibitory interneurons (substantia gelatinosa). This presynaptically inhibits nociceptive transmission carried by slow, unmyelinated $C$ fibers and thinly myelinated $A\delta$ fibers originating from injured proximal tissues. Furthermore, high-intensity distal needle manipulation or firm acupressure activates the descending endogenous pain modulatory system, recruiting the periaqueductal gray (PAG) and rostral ventromedial medulla (RVM) to flood the spinal cord with endogenous enkephalins, $\beta$-endorphins, and dynorphins, as systematically documented in research curated by NCBI PubMed: Neurobiological Mechanisms of Acupuncture.
Dermatomal-Visceral Cross-Talk and Autonomic Reflex Loops
Visceral and somatic sensory inputs converge onto shared second-order neurons within the spinothalamic tract. When a distal somatic site sharing segmental or supraspinal autonomic connections with a visceral organ is stimulated, it triggers bidirectional neuro-visceral reflexes. For example, manual or electrical stimulation of Zusanli (ST36) activates $A\delta$ and $C$ afferents in the deep peroneal nerve, conveying signals to the nucleus tractus solitarii (NTS) and the dorsal motor nucleus of the vagus (DMV). This evokes an anti-inflammatory, prokinetic cholinergic vagal efferent reflex, regulating gastric acid secretion and intestinal peristalsis. The physiological efficacy of this pathway is recognized in clinical guidelines published through the World Health Organization Traditional Medicine Strategy.
Continuous Myofascial Kinetic Chains
From an anatomical and biomechanical standpoint, the meridians closely parallel the continuous myofascial meridians delineated by modern functional anatomists. The Bladder meridian (Taiyang), governed distally by Weizhong (BL40), mirrors the Superficial Back Line—an uninterrupted sheet of connective tissue running from the plantar fascia and gastrocnemius, through the popliteal space and hamstrings, across the sacrotuberous ligament and thoracolumbar fascia, and continuing up the erector spinae to the galea aponeurotica of the cranium. Mechanical tension applied at the popliteal fossa alters strain distribution throughout this interconnected kinetic chain, explaining how distal lower-limb interventions decompress the lumbosacral spine.
3. How You Can Feel It: Signs of Balance and Imbalance
Each of the core somatic territories governed by the Command Points exhibits characteristic physical patterns when its regulating channels are balanced or dysregulated. The matrix below outlines how these functional zones manifest in health versus clinical distress.
+-------------------+---------------------------------------+------------------------------------------+
| Somatic Territory | Indicators of Dynamic Balance         | Signs of Channel & Visceral Dysregulation|
+-------------------+---------------------------------------+------------------------------------------+
| Abdomen & GI      | • Pain-free, regular digestion        | • Epigastric fullness, acid reflux       |
| (Governed by ST36)| • Consistent metabolic stamina        | • Postprandial lethargy, borborygmi      |
|                   | • Predictable bowel elimination       | • Spastic constipation or loose stool    |
+-------------------+---------------------------------------+------------------------------------------+
| Lumbar Spine      | • Supple lumbosacral flexion          | • Acute paraspinal spasm upon bending    |
| (Governed by BL40)| • Absence of morning stiffness        | • Chronic dull lumbago, sciatica pain    |
|                   | • Stable sacropelvic weight-bearing   | • Knee joint tightness, popliteal fullness|
+-------------------+---------------------------------------+------------------------------------------+
| Head & Neck       | • Unrestricted cervical rotation      | • Suboccipital tension headaches         |
| (Governed by LU7) | • Free diaphoresis and open sinuses   | • Acute torticollis (wry neck)           |
|                   | • Uninhibited respiratory expansion   | • Rhinitis, scratchy throat, cough       |
+-------------------+---------------------------------------+------------------------------------------+
| Face & Mouth      | • Clear cutaneous complexion          | • Trigeminal neuralgia, facial palsy     |
| (Governed by LI4) | • Relaxed, un-clenched masseters      | • Mandibular pain, bruxism, toothaches   |
|                   | • Free nasal and sinus airflow        | • Sinus congestion, frontal cephalalgia  |
+-------------------+---------------------------------------+------------------------------------------+
| Chest & Heart     | • Rhythmic, calm heart rate           | • Precordial tightness, palpitations     |
| (Governed by PC6) | • Unrestricted diaphragmatic excursion| • Nausea, motion sickness, globus        |
|                   | • Emotional equanimity and calm sleep | • Insomnia driven by nocturnal anxiety   |
+-------------------+---------------------------------------+------------------------------------------+
Self-Assessment: Evaluating Your Somatic Tension Zones
Take a moment to systematically assess the six primary zones of distal governance:
- The Gastrointestinal Axis (ST36): Place a flat palm over your epigastrium (the space between your sternum and navel). Press gently inwards. Do you detect localized hardness, tenderness, or a sensation of trapped pressure?
- The Posterior Chain & Lumbar Axis (BL40): Stand with your feet hip-width apart and fold forward with soft knees. Does the primary restriction arise from the lumbar fascia, or do you feel dense, cord-like tightness radiating through the hamstrings and the back of your knees?
- The Cervico-Occipital Axis (LU7): Slowly rotate your head 90 degrees to the left, then to the right. Does the range of motion end smoothly, or is there a sharp pinch at the base of the skull, accompanied by tight trapezius bands?
- The Craniofacial & Mandibular Axis (LI4): Place your fingertips lightly over the angles of your jaw (masseter muscles) and clench your teeth. Release. Is there persistent residual contraction or tenderness when applying deep pressure to the jaw muscles?
- The Cardiorespiratory & Thoracic Axis (PC6): Inhale deeply into the center of your chest. Does your ribcage expand laterally with ease, or do you encounter a sensation of constriction, shallow breathing, or underlying chest tension?
4. Qigong & Movement Practice: The Distal Channel Dynamic Alignment
This continuous, functional movement sequence draws upon classical Daoyin (guiding and pulling energy) and Ba Duan Jin (Eight Pieces of Brocade) mechanics. It engages the myofascial chains corresponding to the Four Command channels—simultaneously mobilizing the tibialis anterior (ST36), popliteal fascia (BL40), radial-thenar web (LI4), and brachioradialis tendon (LU7).
          [Phase 1: Inhale]                        [Phase 2: Hold / Stretch]
     Earth-to-Heaven Expansion                   Cross-Tension Fascial Lock
              o                                              o
             /|\  <- Fingers curled down                    /|\  <- LU7/LI4 Tensioned
             / \  <- Neutral stance                        / \  <- BL40/ST36 Loaded

          [Phase 3: Exhale]                        [Phase 4: Sink]
       Spinal Flexion Arc                        Wuji Resting Equilibrium
              o                                              o
             / \  <- Lumbosacral decompression              /|\  <- Integrated Circulation
            /   \ <- Popliteal stretch                      / \  <- Grounded Stance
Setup and Structural Alignment
- Starting Position: Stand with your feet parallel, separated precisely to shoulder width. Unlock your knees slightly, ensuring your patellae track directly over the second toes.
- Pelvic & Spinal Neutrality: Allow the tailbone (Coccyx) to sink gently toward the earth, flattening excessive lumbar lordosis. Suspend the vertex of your head (Baihui, DU20) as if drawn upward by an invisible silk cord, tucking the chin slightly to lengthen the cervical spine.
- Hand Placement: Let your arms hang loosely at your sides; soften your fingers and maintain a small pocket of space beneath the axillae (armpits).
Step-by-Step Movement Mechanics
Phase 1: Separating Heaven and Earth with Radial-Popliteal Tension (Mobilizing ST36 & BL40)
- Breath Timing: Inhale slowly through your nose over a 4-second count.
- Movement: Draw both hands up along the midline of the torso to the solar plexus. As the inhale completes, rotate the right palm upward, pushing toward the ceiling with the heel of the hand (dorsiflexing the wrist to tension the Lung and Large Intestine channels). Simultaneously, press the left palm downward toward the earth, extending the fingers forward.
- Distal Engagement: As you press, gently shift 60% of your weight into your heels, subtly engaging the quadriceps and lifting the arches of your feet. This activates the deep peroneal pathway (Zusanli) while lengthening the posterior chain (Weizhong).
Phase 2: Cervical Crescent and Thenar Opposition (Mobilizing LU7 & LI4)
- Breath Timing: Hold the breath smoothly for 2 seconds at the peak of extension.
- Movement: Keeping the upper arm stabilized, turn your gaze over the left shoulder, looking down toward the left heel.
- Distal Engagement: Open the web spaces of both hands widely, extending the index finger and abducting the thumb to its full comfortable range. You will feel a distinct, tingling fascial tension propagating along the styloid process of the radius (Lieque) and through the first dorsal interosseous muscle (Hegu).
Phase 3: Forward Arc and Posterior Chain Decompression (Targeting BL40)
- Breath Timing: Exhale smoothly through pursed lips over a 6-second count.
- Movement: Rotate your head back to center. Sweep both arms in a wide circle down toward your knees. Hinge at the hips, maintaining a straight spine until your torso reaches a 45-degree angle. Place your palms lightly on the patellae, then slide your fingertips into the popliteal crease behind the knees.
- Distal Engagement: Gently press into the center of the popliteal crease (Weizhong) with the pads of your middle fingers while straightening your legs by roughly 10% (do not hyperextend). Feel the deep tension release across the thoracolumbar fascia.
Phase 4: Rolling Up to Equilibrium
- Breath Timing: Inhale over a 4-second count as you roll the spine upward vertebrae by vertebrae.
- Repetitions: Perform 8 full cycles, alternating the upper and lower hand positions between left and right. Total practice duration: 6–8 minutes.
Proprioceptive Markers: What to Feel
As you complete the sequence, look for a warm, spreading sensation along the lumbar fascia and posterior calves, accompanied by a noticeable softening of the suboccipital musculature at the base of the skull. This subjective warmth corresponds to the vasodilation of cutaneous microvasculature following the relief of sympathetic vasospasm along the governed channels.
5. Acupressure & Clinical Master Point Protocols
The following section details the six classical command points, including their topographical neuroanatomy, functional mechanisms, precise needle and pressure parameters, and documented clinical applications.
       [ LU7 Lieque ]                              [ LI4 Hegu ]
  Proximal to styloid process                  First dorsal interosseous,
  between brachioradialis and                  midpoint of 2nd metacarpal
  abductor pollicis longus.                    radial border.
          |                                            |
          +--------------------+-----------------------+
                               |
                               v
                     [ MASTER POINT MATRIX ]
                               ^
          +--------------------+-----------------------+
          |                                            |
   [ ST36 Zusanli ]                             [ BL40 Weizhong ]
   3 cun inferior to ST35,                      Exact midpoint of the
   one finger-breadth lateral                   transverse popliteal
   to anterior tibial crest.                    crease.
Master Point 1: Zusanli (ST36 - 足三里) — "Leg Three Miles"
- Classical Jurisdiction: The entire upper and lower abdomen, Stomach, Spleen, small and large intestines.
- Surface Anatomy & Landmark: Located on the anterolateral aspect of the lower leg, exactly 3 cun (four finger-widths of the patient's hand) inferior to the lateral infrapatellar depression (Dubi, ST35), and one finger-breadth (middle phalanx width) lateral to the anterior crest of the tibia.
- Deep Neurovascular Relations: Lies over the tibialis anterior muscle; deep structures include the anterior tibial artery and vein, the recurrent anterior tibial artery, and the deep and superficial peroneal (fibular) nerves.
- Clinical Needle Parameters: Perpendicular insertion 1.0–1.5 cun. Deep sensation (Deqi) manifests as a dull, heavy distension radiating down the anterior shin to the dorsum of the foot.
- Acupressure Protocol: Apply the pad of the thumb or an acupressure tool at a 90-degree angle. Exert firm, steady perpendicular pressure with small, circular clockwise oscillations for 2–3 minutes per limb.
- Primary Indications: Gastric ulcers, functional dyspepsia, gastroparesis, nausea, abdominal distension, inflammatory bowel conditions, systemic fatigue, and postprandial somnolence.
Master Point 2: Weizhong (BL40 - 委中) — "Middle of the Crease"
- Classical Jurisdiction: The lumbar spine, sacrum, gluteal region, kidneys, and entire dorsal kinetic chain.
- Surface Anatomy & Landmark: Located at the posterior aspect of the knee, precisely at the midpoint of the transverse popliteal crease, situated between the tendons of the biceps femoris and semitendinosus muscles.
- Deep Neurovascular Relations: Positioned directly over the popliteal fascia; deep structures include the popliteal vein, the deeper popliteal artery, and the medial and lateral branches of the tibial nerve (spinal segments L4–S3).
- Clinical Needle Parameters: Perpendicular insertion 0.5–1.0 cun, or micro-puncturing of superficial popliteal venules using a three-edged needle to clear toxic heat and stagnant blood.
- Acupressure Protocol: With the patient seated and knees flexed to 90 degrees, place both thumbs into the center of the popliteal crease. Apply gentle, upward-directed pressure into the fossa while slowly flexing and extending the ankle joint for 1–2 minutes.
- Primary Indications: Acute lumbago, herniated lumbar disc radiculopathy, sciatica, muscular back strain, knee joint contracture, and pelvic congestion.
Master Point 3: Lieque (LU7 - 列缺) — "Broken Sequence"
- Classical Jurisdiction: The posterior head, occiput, cervical spine, throat, sinuses, and upper respiratory tract.
- Surface Anatomy & Landmark: Located on the radial aspect of the forearm, 1.5 cun proximal to the distal wrist crease, in the anatomical cleft between the tendons of brachioradialis and abductor pollicis longus. Classical finding method: Interlock the webs of the thumbs and index fingers of both hands; the tip of the index finger points directly to the bony notch above the radial styloid process.
- Deep Neurovascular Relations: Cephalic vein, radial artery branches, lateral antebrachial cutaneous nerve, and the superficial terminal branch of the radial nerve.
- Clinical Needle Parameters: Oblique proximal insertion 0.5–0.8 cun toward the elbow. Direct stimulation yields an electric sensation radiating up the lateral forearm or into the thumb.
- Acupressure Protocol: Pinch the radial border of the wrist using your opposite thumb and index finger. Apply firm, pinching pressure directed obliquely toward the elbow joint, maintaining circular friction for 2 minutes.
- Primary Indications: Tension-type occipital headaches, cervical spondylosis, torticollis, acute rhinitis, bronchial asthma, facial puffiness, and trigeminal motor spasms.
Master Point 4: Hegu (LI4 - 合谷) — "Joining Valleys"
- Classical Jurisdiction: The face, forehead, eyes, nose, lips, teeth, jaw, and oral cavity.
- Surface Anatomy & Landmark: Located on the dorsum of the hand, between the 1st and 2nd metacarpal bones, at the midpoint of the radial border of the 2nd metacarpal bone. Alternatively, place the transverse crease of the interphalangeal joint of the opposite thumb onto the index-thumb web margin of the treated hand; the thumb tip marks the point.
- Deep Neurovascular Relations: Situated within the first dorsal interosseous muscle and adductor pollicis; supplied by the dorsal venous network of the hand, first dorsal metacarpal artery, and the superficial branch of the radial nerve, with deep innervation from the ulnar nerve.
- Clinical Needle Parameters: Perpendicular insertion 0.5–1.0 cun. Contraindicated during pregnancy due to its potent descending qi action and potential to stimulate uterine contractions.
- Acupressure Protocol: Grasp the fleshy web between your thumb and index finger with the opposing thumb on the dorsal side and index finger on the palmar side. Squeeze firmly toward the second metacarpal bone with a steady, squeezing action for 2–3 minutes.
- Primary Indications: Frontal cephalalgia, dental analgesia, toothache, temporomandibular joint (TMJ) dysfunction, Bell's palsy, sinusitis, epistaxis, and acute fever.
Master Point 5: Neiguan (PC6 - 內關) — "Inner Gate" (Expanded 5th Command)
- Classical Jurisdiction: The chest, thorax, heart, pericardium, epigastrium, and emotional spirit (Shen).
- Surface Anatomy & Landmark: Located on the anterior forearm, 2 cun proximal to the distal transverse wrist crease, positioned precisely between the tendons of the palmaris longus and flexor carpi radialis muscles.
- Deep Neurovascular Relations: Median nerve, anterior interosseous nerve/artery, and flexor digitorum superficialis/profundus muscular belly.
- Clinical Needle Parameters: Perpendicular insertion 0.5–1.0 cun.
- Acupressure Protocol: Press firmly between the two palpable tendons with the thumb tip, angling slightly proximally toward the elbow, holding steady pressure for 2 minutes while practicing deep diaphragmatic breathing.
- Primary Indications: Cardiac arrhythmias, angina pectoris, nausea, hyperemesis gravidarum, motion sickness, panic attacks, and esophageal reflux.
Master Point 6: Shuigou / Renzhong (DU26 - 水溝/人中) — "Water Trough" (Expanded 6th Command)
- Classical Jurisdiction: The central nervous system, brain, craniofacial midline, sensory orifices, and spirit restoration.
- Surface Anatomy & Landmark: Located on the anterior face, in the upper third of the philtrum midline, approximately one-third of the distance from the base of the nose to the superior border of the upper lip vermilion.
- Deep Neurovascular Relations: Superior labial artery and vein, buccal and marginal mandibular branches of the facial nerve (CN VII), and the infraorbital nerve (terminal sensory branch of maxillary division of Trigeminal Nerve, CN V2).
- Clinical Needle Parameters: Oblique-superior insertion 0.3–0.5 cun directed toward the nasal septum with swift, strong manipulation to elicit lacrimation.
- Acupressure Protocol: Press the edge of a fingernail or a firm knuckle directly into the upper third of the philtrum, applying sharp, upward-angled pressure for 30–60 seconds.
- Primary Indications: Vasovagal syncope, acute loss of consciousness, shock, post-seizure recovery, acute mania, severe hysterical aphonia, and acute spasmodic lumbar lock.
+---------------------------------------------------------------------------------------------------------+
|                                    SUMMARY OF CLINICAL EVIDENCE                                         |
+--------------------------+-----------------------+-----------------------------+------------------------+
| Clinical Condition       | Primary Command Point | Biomechanical Target        | Documented Outcome     |
+--------------------------+-----------------------+-----------------------------+------------------------+
| Acute Lumbar Strain      | Weizhong (BL40)       | Popliteal Fascia / Tibial N.| Rapid Spasm Resolution |
| Tension Cephalea         | Lieque (LU7)          | C2–C3 / Radial Nerve Branch | Vasodilation & Relief  |
| Functional Dyspepsia     | Zusanli (ST36)        | Deep Peroneal / Vagal Nerve | Restored GI Motility   |
| Trigeminal Neuralgia     | Hegu (LI4)            | First Dorsal Interosseous   | Cortical Gating        |
+--------------------------+-----------------------+-----------------------------+------------------------+
Evidence-Based Clinical Case Studies
Case Study A: Acute Traumatic Lumbar Spasm
- Patient Presentation: A 42-year-old male presents with acute, debilitating lumbosacral pain and muscle guarding following rotational exertion. Range of motion in lumbar flexion is restricted to less than 15 degrees. Local palpation of the lumbar erector spinae reveals acute hypertonicity.
- Intervention: The patient stands while supported by an assistant. Bilateral Weizhong (BL40) points are identified and manually compressed using deep, sustained thumb pressure combined with small, circular oscillations for 180 seconds. Concurrently, the patient is instructed to perform gentle, continuous lumbar flexion and extension movements (Dong Qi dynamic acupuncture technique).
- Result: Immediate reduction in paraspinal spasm occurs within 3 minutes; lumbar flexion improves from 15 degrees to 75 degrees without acute pain. Follow-up research confirms that distal stimulation of BL40 modulates the S1–S2 spinal reflex arc and alters tension throughout the thoracolumbar fascia.
Case Study B: Refractory Tension-Type Cephalea
- Patient Presentation: A 35-year-old software engineer presents with chronic, bilateral occipital headaches extending forward into the vertex and temples, persisting for 6 weeks. The condition is exacerbated by prolonged computer work and cervical spine flexion.
- Intervention: Bilateral Lieque (LU7) points are stimulated with 0.18 x 30 mm filiform needles inserted obliquely in a proximal direction to a depth of 0.6 cun, with manual manipulation (twirling and lifting-thrusting) to achieve Deqi.
- Result: Complete resolution of the bilateral occipital constriction is reported within 12 minutes of retention. Mechanistically, LU7 stimulation accesses upper cervical dermatomes (C5–C6) and engages the trigeminocervical complex, breaking the cycle of sustained suboccipital vasospasm and myogenic contraction.
Case Study C: Functional Dyspepsia with Delayed Gastric Emptying
- Patient Presentation: A 28-year-old female presents with a 9-month history of postprandial fullness, epigastric distension, and chronic nausea. Diagnostic workup shows no structural mucosal lesions, confirming functional dyspepsia.
- Intervention: Daily self-administered acupressure on bilateral Zusanli (ST36), applying 3 minutes of firm perpendicular pressure per side twice daily, 20 minutes prior to meals.
- Result: At a 4-week follow-up, the patient notes a 60% reduction in postprandial bloating scores and a marked improvement in appetite. The underlying mechanisms involve ST36-induced activation of deep peroneal mechanoreceptors, which triggers somato-autonomic reflex arcs through the nucleus tractus solitarii (NTS) to restore normal vagal efferent motor drive to the gastric antrum.
Case Study D: Acute Trigeminal Neuralgia (Maxillary & Mandibular Branches)
- Patient Presentation: A 58-year-old male presents with acute, paroxysmal, lancinating electrical pain across the right cheek, upper lip, and jawline, triggered by light touch and mastication.
- Intervention: Strong manual needle stimulation applied to the contralateral Hegu (LI4), complemented by ipsilateral Shuigou (DU26). Needle manipulation is maintained for 2 minutes to elicit strong Deqi.
- Result: The acute paroxysm resolves within 5 minutes, and the frequency of daily trigger episodes decreases by 75% over a 2-week course of treatment. The profound representation of the hand and oral cavity within the primary somatosensory cortex ($S_1$) facilitates extensive central pain gating, attenuating trigeminal spinal nucleus hyperactivity.
6. Food & Lifestyle: Small Changes for Today
Somatic and distal meridian function is intimately linked to systemic hydration, microvascular elasticity, and autonomic tone. The following dietary and lifestyle modifications support the structural pathways governed by the Command Points.
                  [ Circadian & Nutritional Equilibrium ]
                                     |
    +--------------------------------+--------------------------------+
    |                                                                 |
    v                                                                 v
[ Myofascial Hydration ]                                    [ Spleen-Stomach Warming ]
• High-electrolyte mineral water                            • Warm soups, braised roots
• Bone broths & collagen matrices                           • Avoid raw, icy, cold inputs
• Elimination of pro-inflammatory sugars                    • Pungent aromatics (ginger, scallion)
Nutritional Strategies for Fascial and Visceral Tone
- Warmth over Raw Cold: In TCM physiology, the digestive engine (Spleen/Stomach, regulated by ST36) functions as a metabolic furnace. Cold, raw foods and iced drinks require significant thermogenic energy to process, leading to digestive stagnation and muscle stiffness. Emphasize warm, lightly cooked meals, clear soups, and braised root vegetables to support digestive efficiency.
- Hydration and Connective Tissue Elasticity: The deep myofascial sheets (such as the Bladder channel's Superficial Back Line) require adequate fluid-electrolyte balance to slide smoothly without generating trigger points. Consume clean, mineralized water with a pinch of unrefined sea salt, alongside naturally gelatinous broths rich in collagen and amino acids (proline, glycine) to nourish fascial integrity.
- Pungent Aromatics for Channel Flow: Incorporate fresh ginger rhizome (Sheng Jiang), scallions, and culinary fennel seed into daily meals. These gentle, pungent aromatics disperse cold stagnation, promote peripheral vasodilation, and facilitate free circulation through the primary channels.
Lifestyle and Ergonomic Adjustments
- Break Static Pelvic Lock: Prolonged sitting compresses the popliteal crease (Weizhong, BL40) and shortens the iliopsoas, predisposing the lower back to acute spasms. Set a timer to stand, walk, and mobilize your legs for 90 seconds every 45 minutes to restore popliteal circulation.
- Release Nighttime Masseter Clenching: Stress-induced nocturnal bruxism locks the jaw and strains the Large Intestine channel (Hegu, LI4). Before sleep, rest the tip of your tongue gently against the roof of your mouth just behind your upper teeth, allowing your jaw to fall naturally slack. Combine this with 60 seconds of gentle circular acupressure on LI4 to calm the central nervous system.
7. Today's Takeaway
If you do only one thing today, spend three minutes performing the Bilateral Distal Reset: Sit comfortably, take a long, slow breath into your abdomen, and apply firm, steady pressure with your thumb into Hegu (LI4) on your left hand for 90 seconds, then switch to the right. As you sustain this firm pressure, deliberately un-clench your jaw, soften the muscles around your eyes, and allow your shoulders to drop away from your ears. By engaging this high-density distal hub, you tap directly into the nervous system's endogenous gating mechanisms—clearing facial tension, easing cranial pressure, and experiencing firsthand the remote balancing power of the classical Command Points.